Rachel Apa collapsed in Central Park. The cause was rhabdomyolysis, a rare muscle condition that can be brought on by exertion, her father said.
from NYT > Health https://ift.tt/yEJoe9i
from NYT > Health https://ift.tt/yEJoe9i


April Health And Fitness Tips.

Enter April Health And Fitness Tips.

April Health And Fitness Tips.


 November 03, 2026
 Rose
 Health - The New York Times, NYT > Health
 No commentsNovember 03, 2026RoseHealth News, KFF Health NewsNo comments
TAKOMA PARK, Md. — Friday night lights took on a whole new meaning at a high school here in this suburb of Washington, D.C.
Instead of fans packing stadium bleachers to watch football, on this recent October weekend the gymnasium, hallways, and parking areas were jammed with people desperately seeking healthcare at a free pop-up clinic.
The 2026 election season has been punctuated by affordability issues, with polls showing high healthcare costs are a top concern among likely voters. The staggering toll of people struggling to get care was on full display here just eight miles northeast of the U.S. Capitol — in an area where census data shows the median household income tops $108,000 and about 94% have health insurance.
Dozens of people slept in their cars overnight outside Takoma Academy to secure spots for free health, dental, or vision care, according to clinic coordinators and interviews with patients.
Though clinic doors were scheduled to open at 6 a.m. Oct. 17, the first patients drove up shortly before midnight. By 4 a.m., three hours before sunrise, about 80 cars had arrived. Patients were given numbers representing their place in line when they entered the parking lot, and they had to be on site when they were notified by text message that it was their turn.

Kenys Bautista arrived at the school before midnight after driving 20 minutes from her home in Wheaton, Maryland. She wanted to be sure she got the medical and dental checkups that she had put off for three years because she didn’t have insurance or the money to cover the costs.
“It’s really sad that a lot of people like me had to sleep in their car just to see a doctor or dentist because we do not have health insurance,” Bautista said. She works as a payroll specialist for a small company but does not get any health benefits.
Bautista was one of 467 patients at the weekend clinic. Most received dental and/or medical care. Ninety-nine got vision exams, and many left with new eyeglasses, according to clinic organizers.
While most patients at the clinic were uninsured, 1 in 4 had health coverage, such as through Medicare or their employer. But many said just having coverage was not enough, because it left them with unaffordable out-of-pocket costs .
“I never thought I would need a clinic like this, but it’s gotten so expensive in the world,” Alma Walton said. She has Medicare, but routine dental care is not a standard benefit.
Walton, who lives in Camp Springs, Maryland, was 59th in line for care. She arrived around 1:30 a.m. “I wanted to make sure I could get in,” she said. She went to the clinic in hopes of getting a filling fixed after it cracked over the summer. She had postponed seeing a dentist.
Around 11 a.m., Walton was in one of the 30 dental treatment tents set up in the large gymnasium, having her filling replaced.
“You got here just in time,” John Renzi, a dentist volunteering at the clinic, told her just before he began drilling. “Any longer and this tooth would have been a goner.”
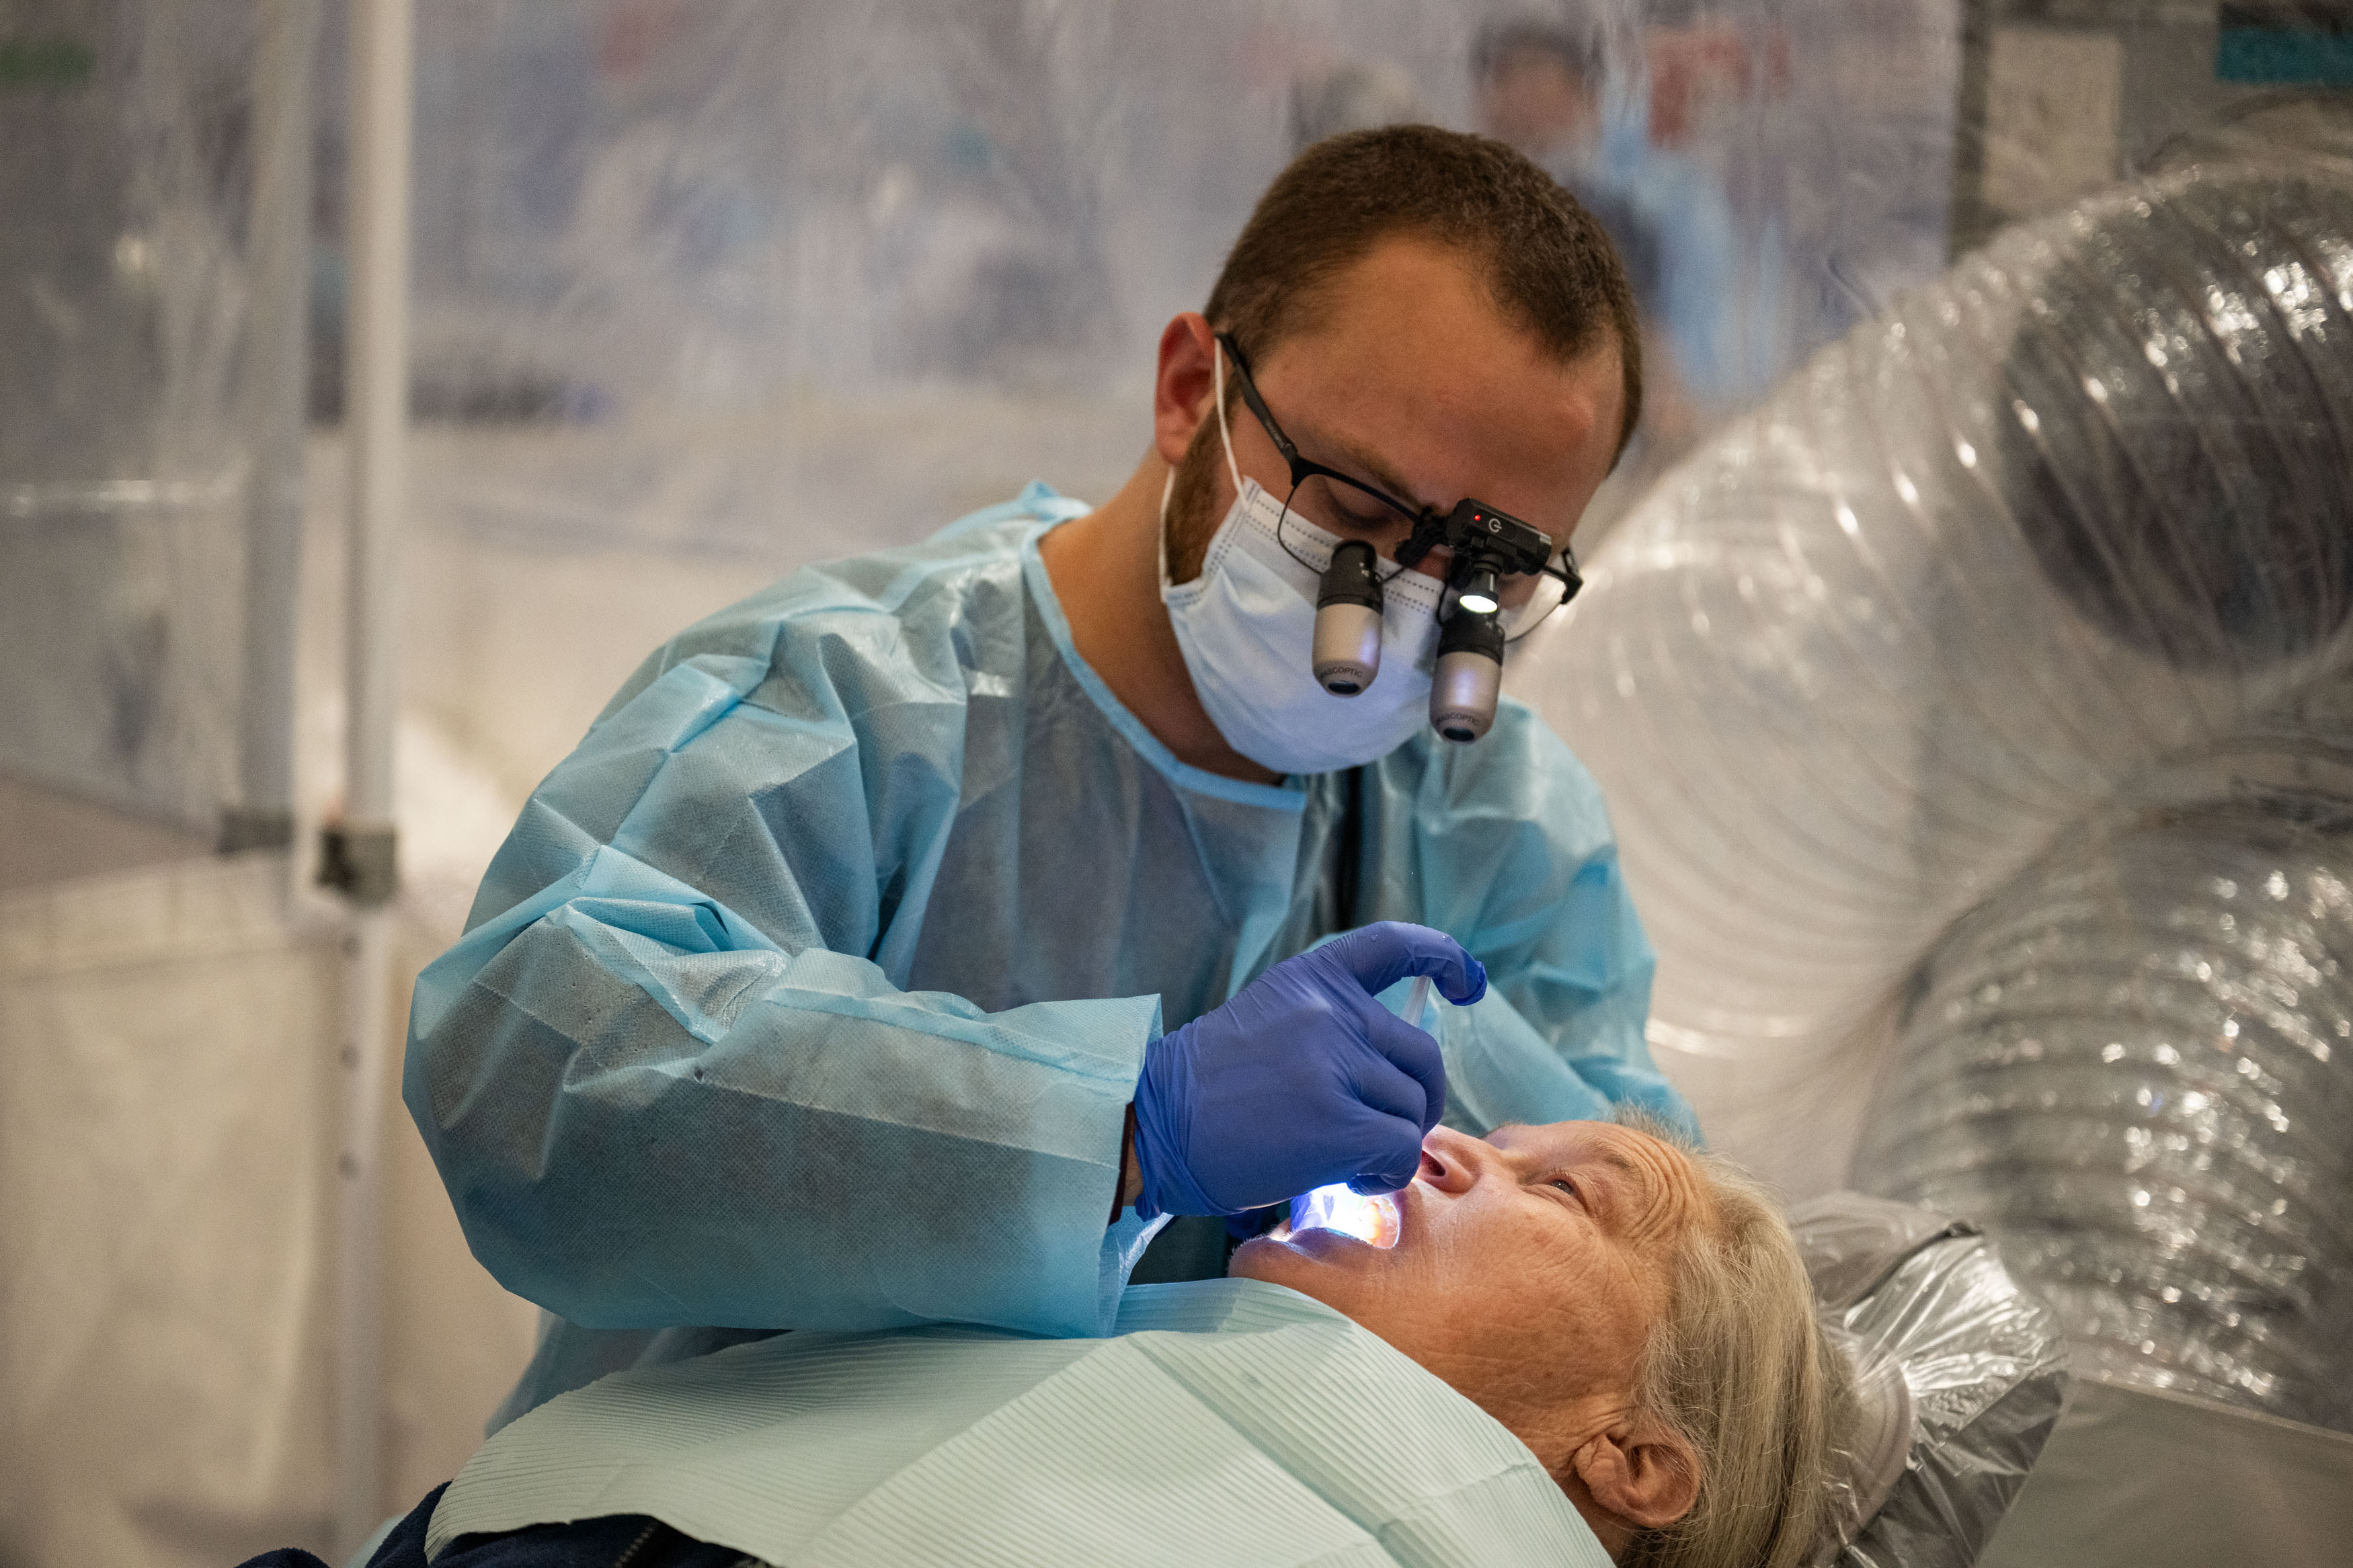
The clinic was organized by Remote Area Medical, a Tennessee-based nonprofit that says it has provided free healthcare to more than a million patients over its 40-year history. The clinics initially targeted rural areas, such as in Appalachia, traditionally home to some of the poorest and least insured communities in the country.
In recent years, the organization has branched out into urban and suburban areas — such as around the nation’s capital, Baltimore, and Philadelphia — where having insurance is more common. The clinics rely on doctors and dentists donating their time.
At the Takoma Park event, more than 300 dental, medical, and vision professionals volunteered along with members of the U.S. Public Health Service.
According to a survey by Remote Area Medical, nearly 40% of patients here said they had not seen a dental provider — other than one provided at a RAM clinic — in at least two years.
And nearly two-thirds said they did not have a usual place for seeking care other than a hospital emergency room.


Dana Bensinger, a nurse specialist working at the medical care clinic, said many patients had high blood pressure or diabetes. They were given prescriptions for a 90-day supply of pills and told to connect with community health centers or free clinics where they can get free or low-cost primary care.
“We have seen a lot of folks who lose insurance or are not able to keep it, and so they can’t get their prescriptions renewed,” he said.
Many patients at the clinic showed up to get a tooth extraction — and with it, relief from dental pain.
“We call it point-and-pull dentistry,” said Tom Ritter, a retired dentist who was triaging dental patients. “You point to the tooth you want out, and we take it out.”
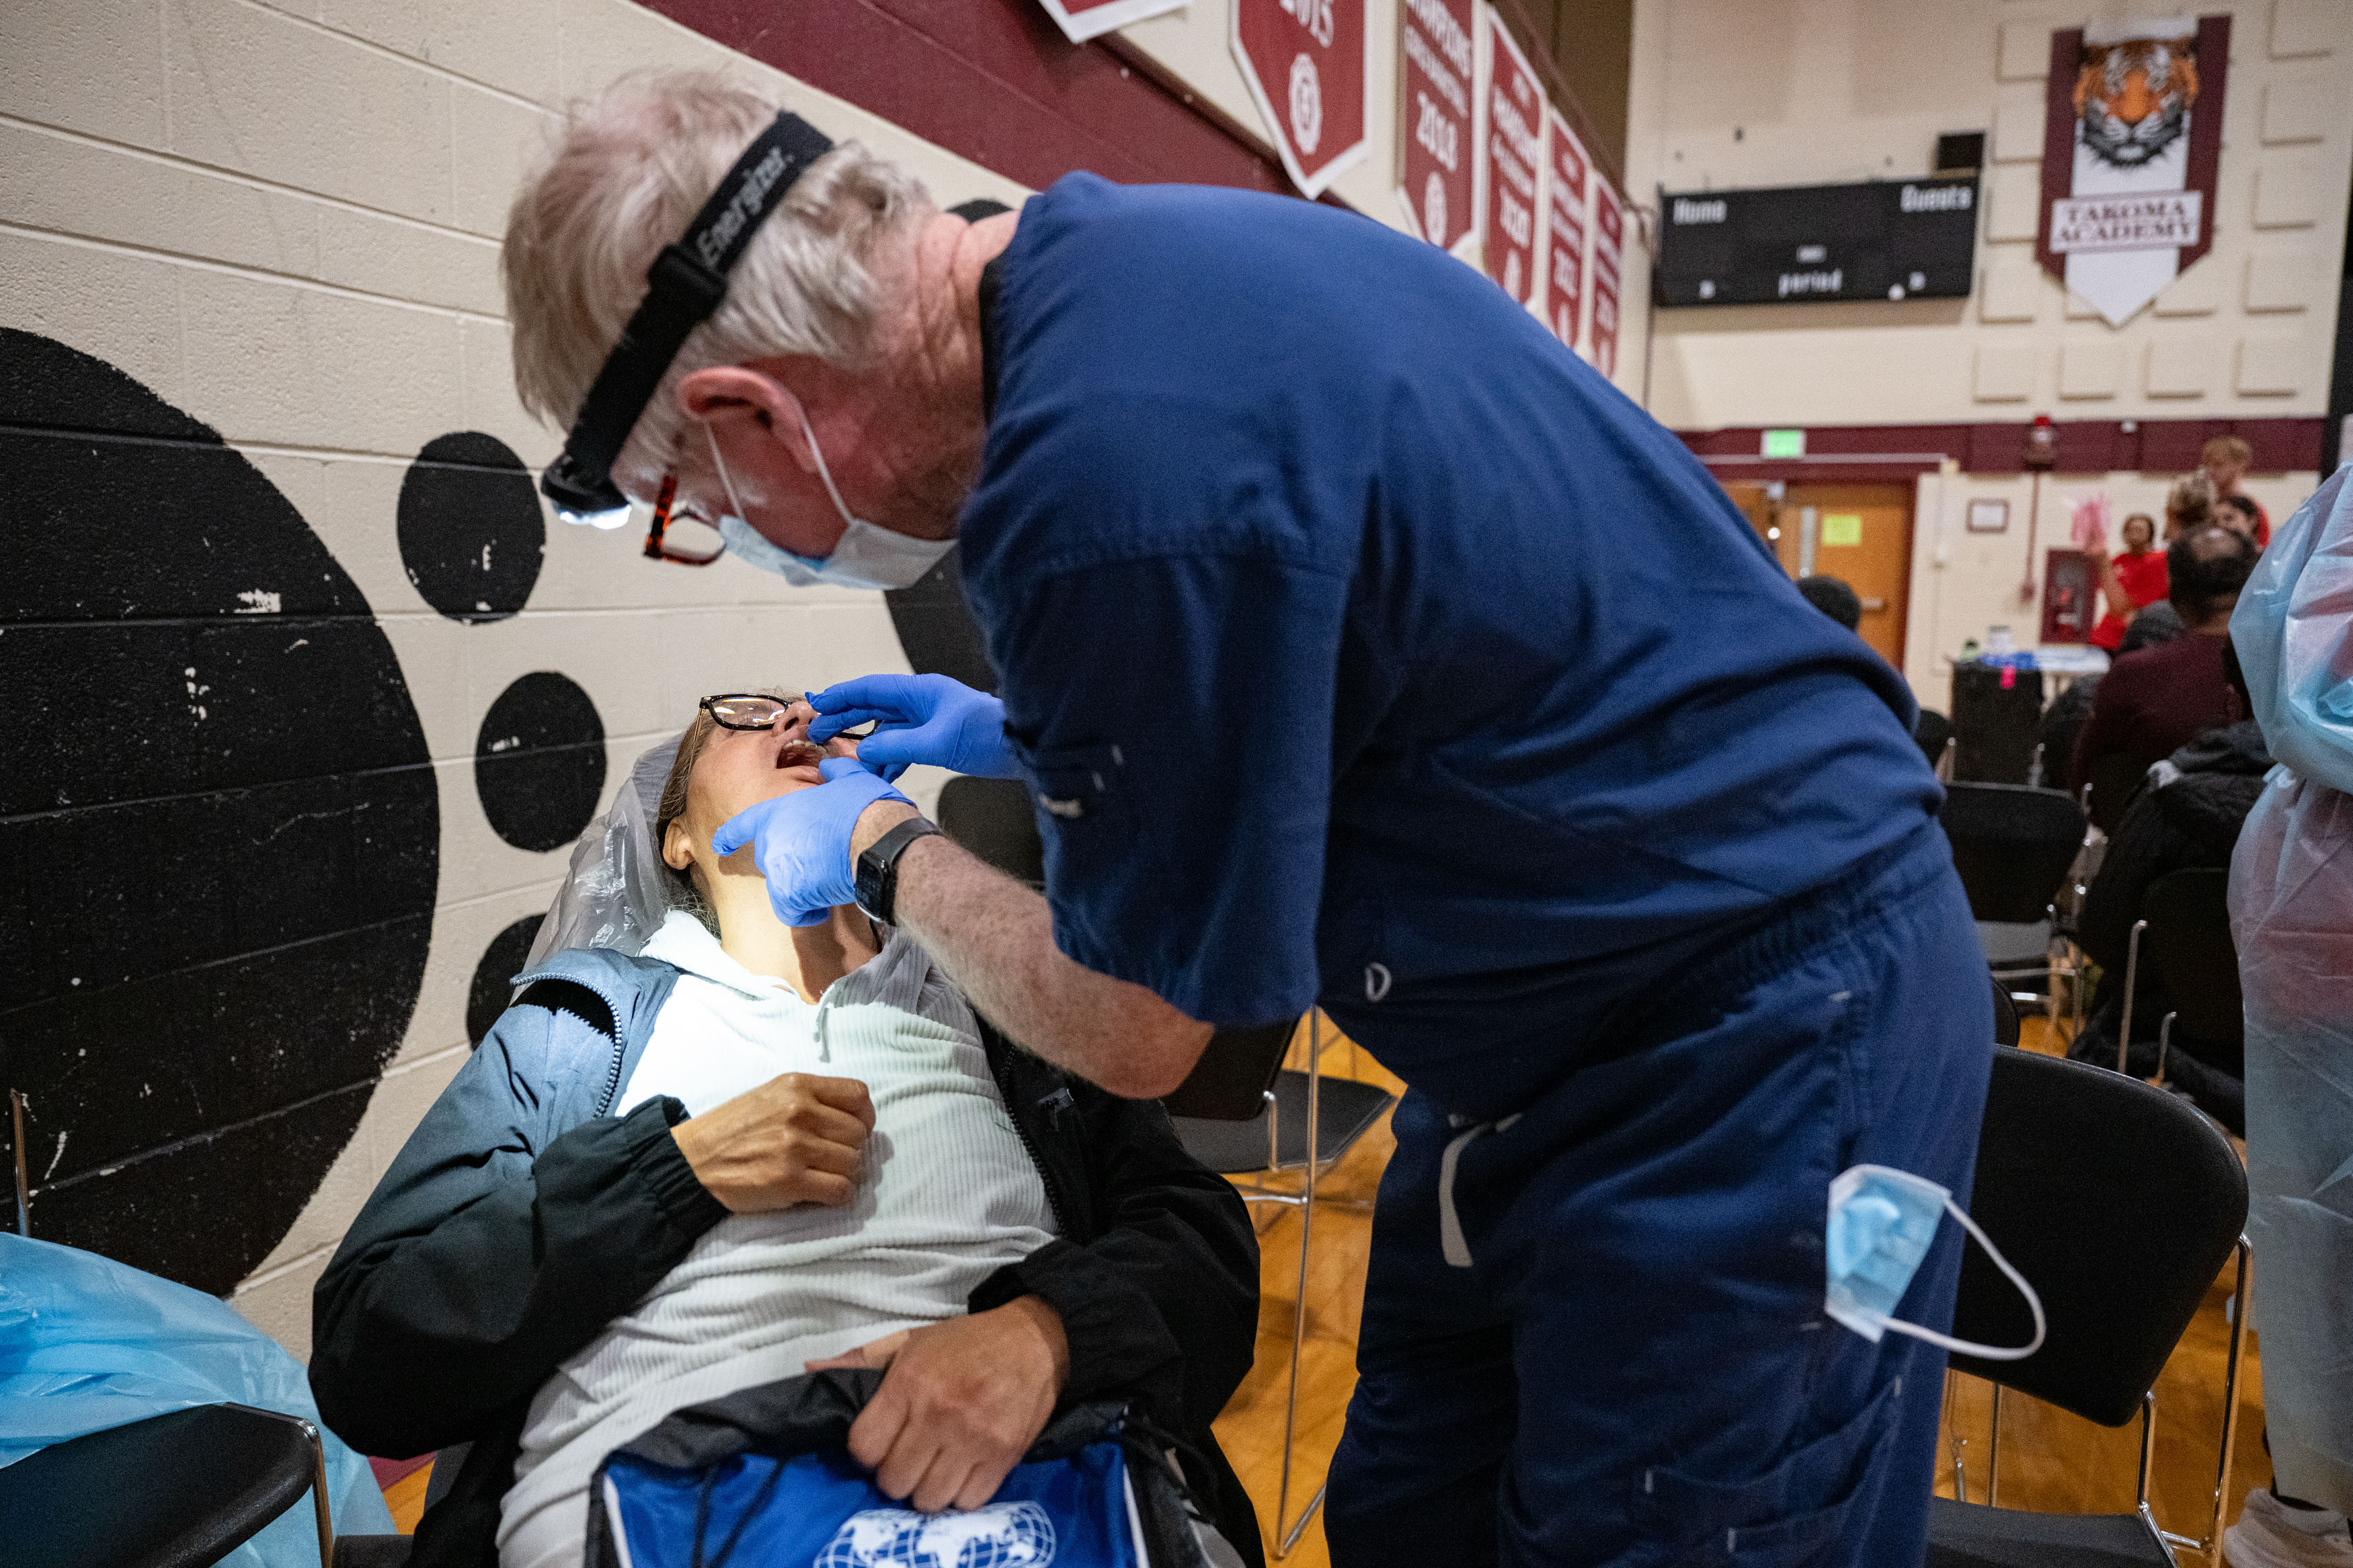
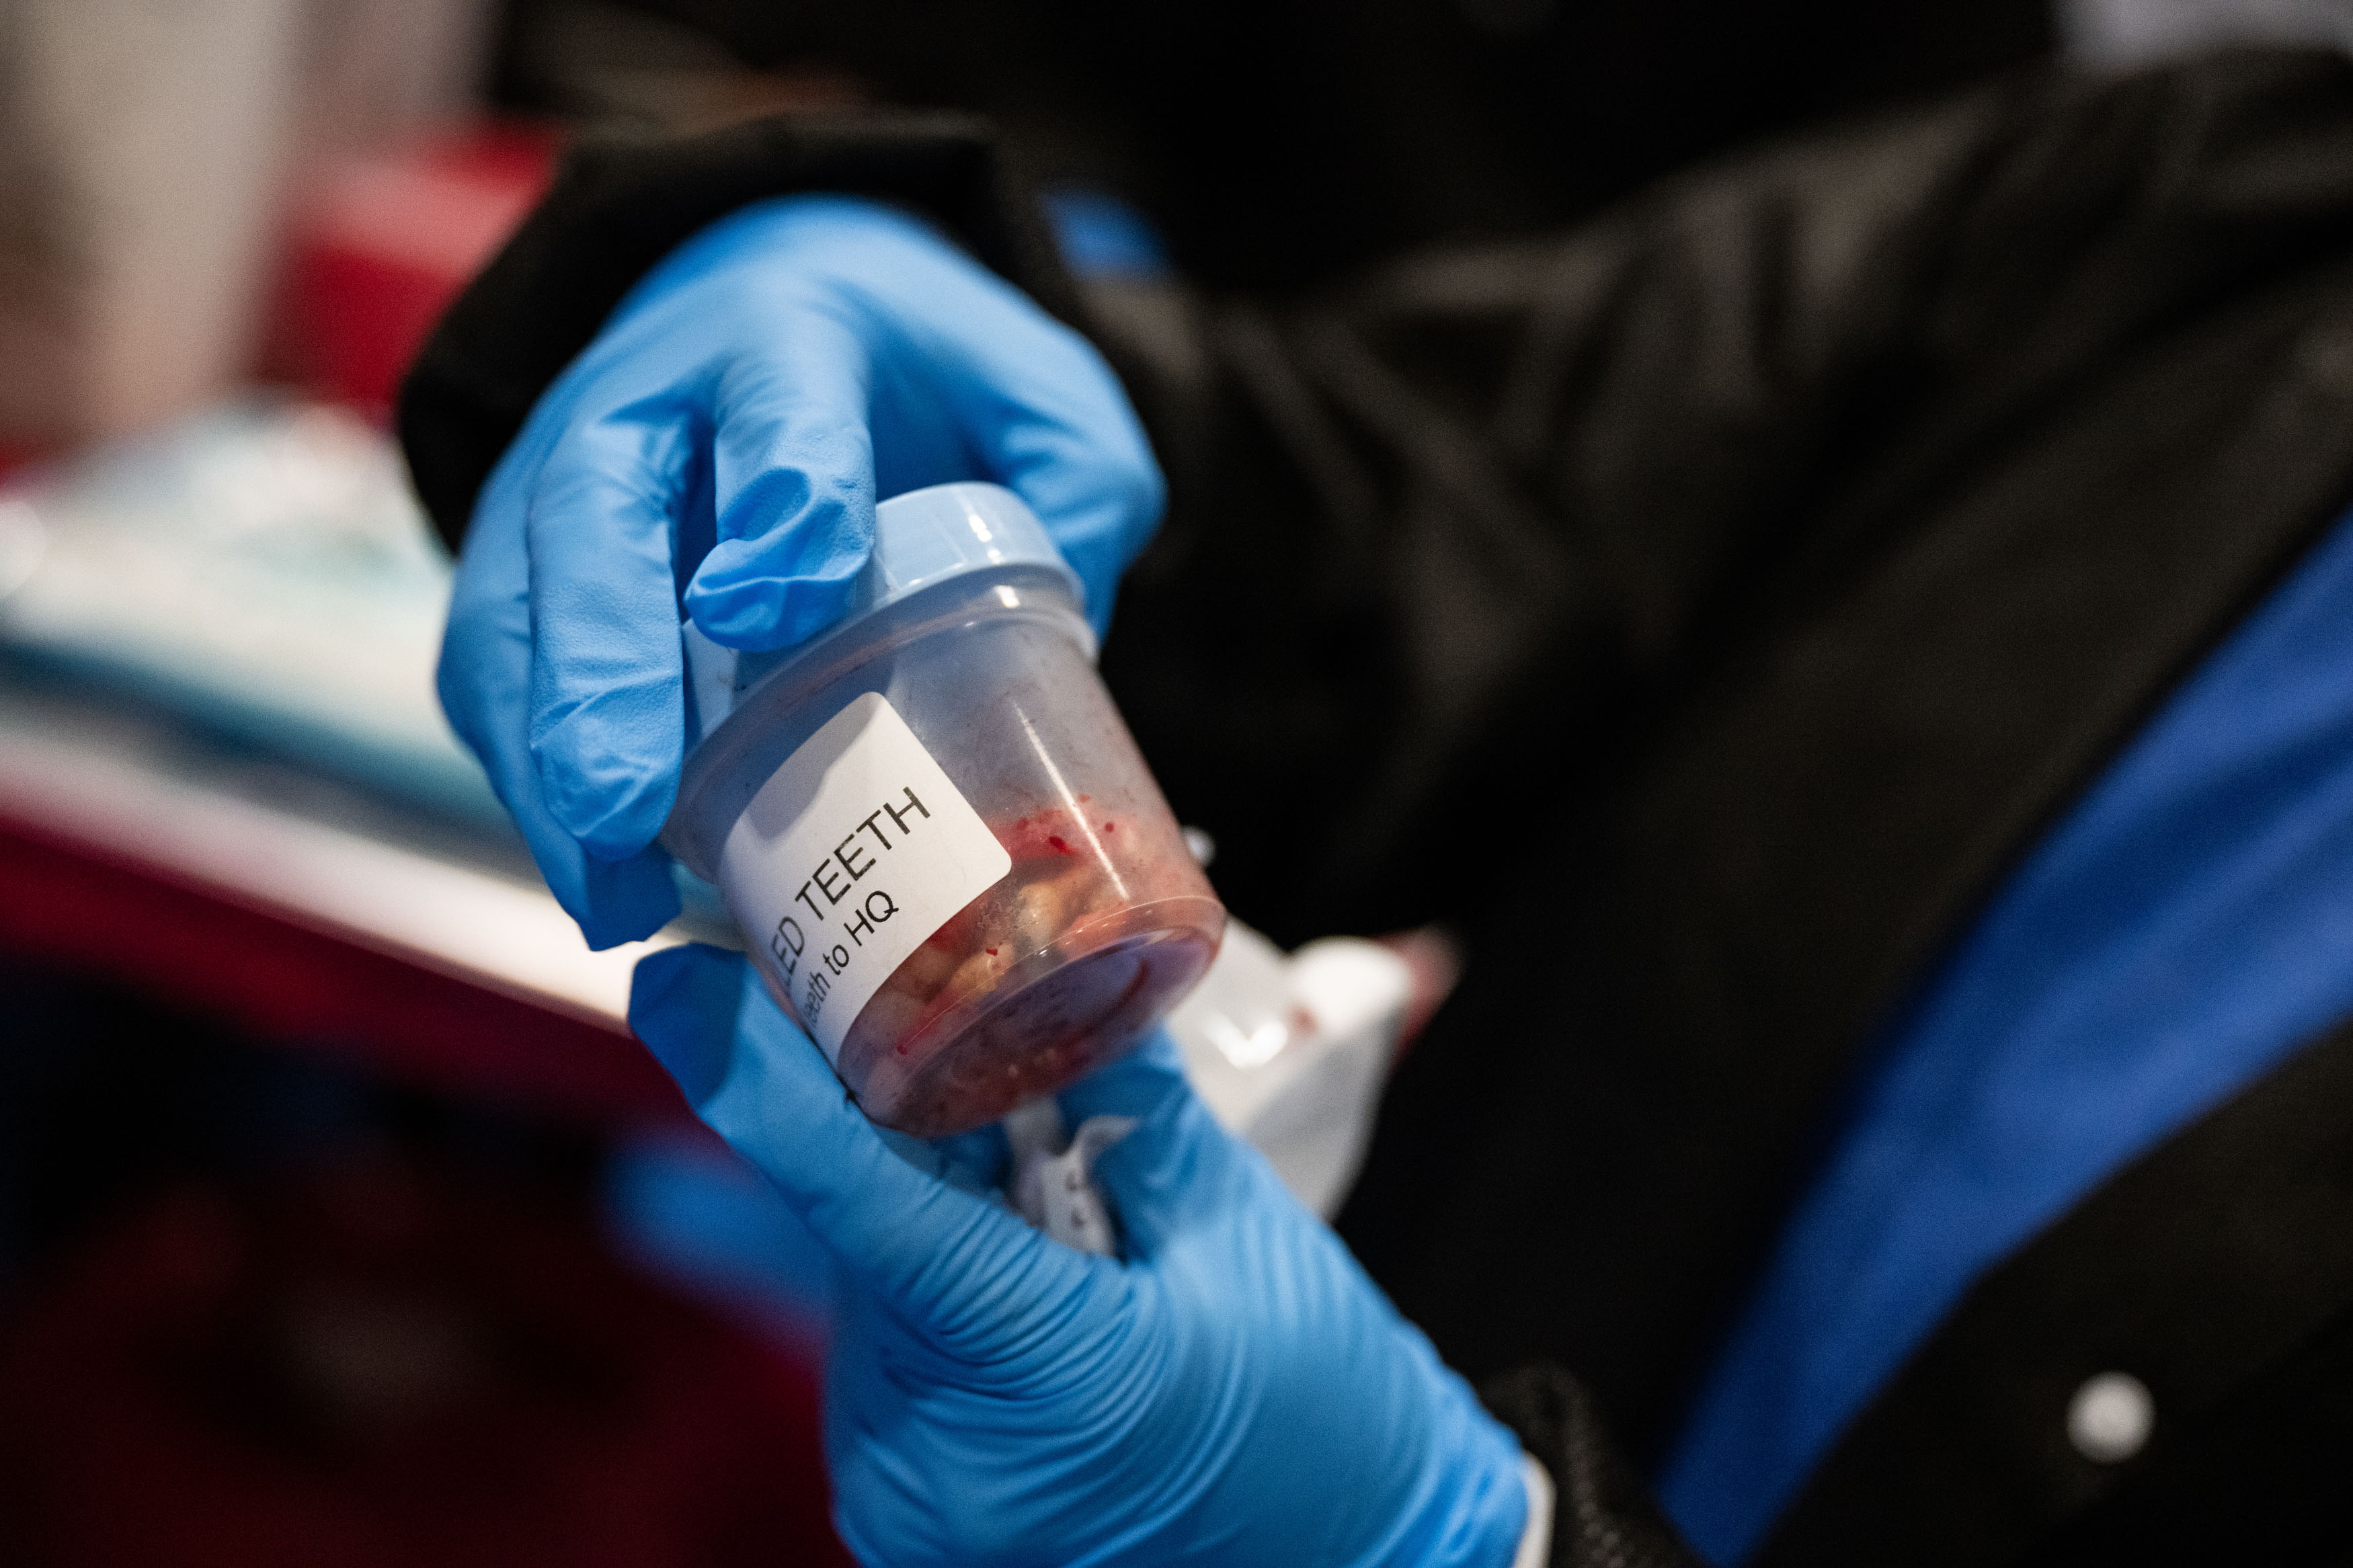
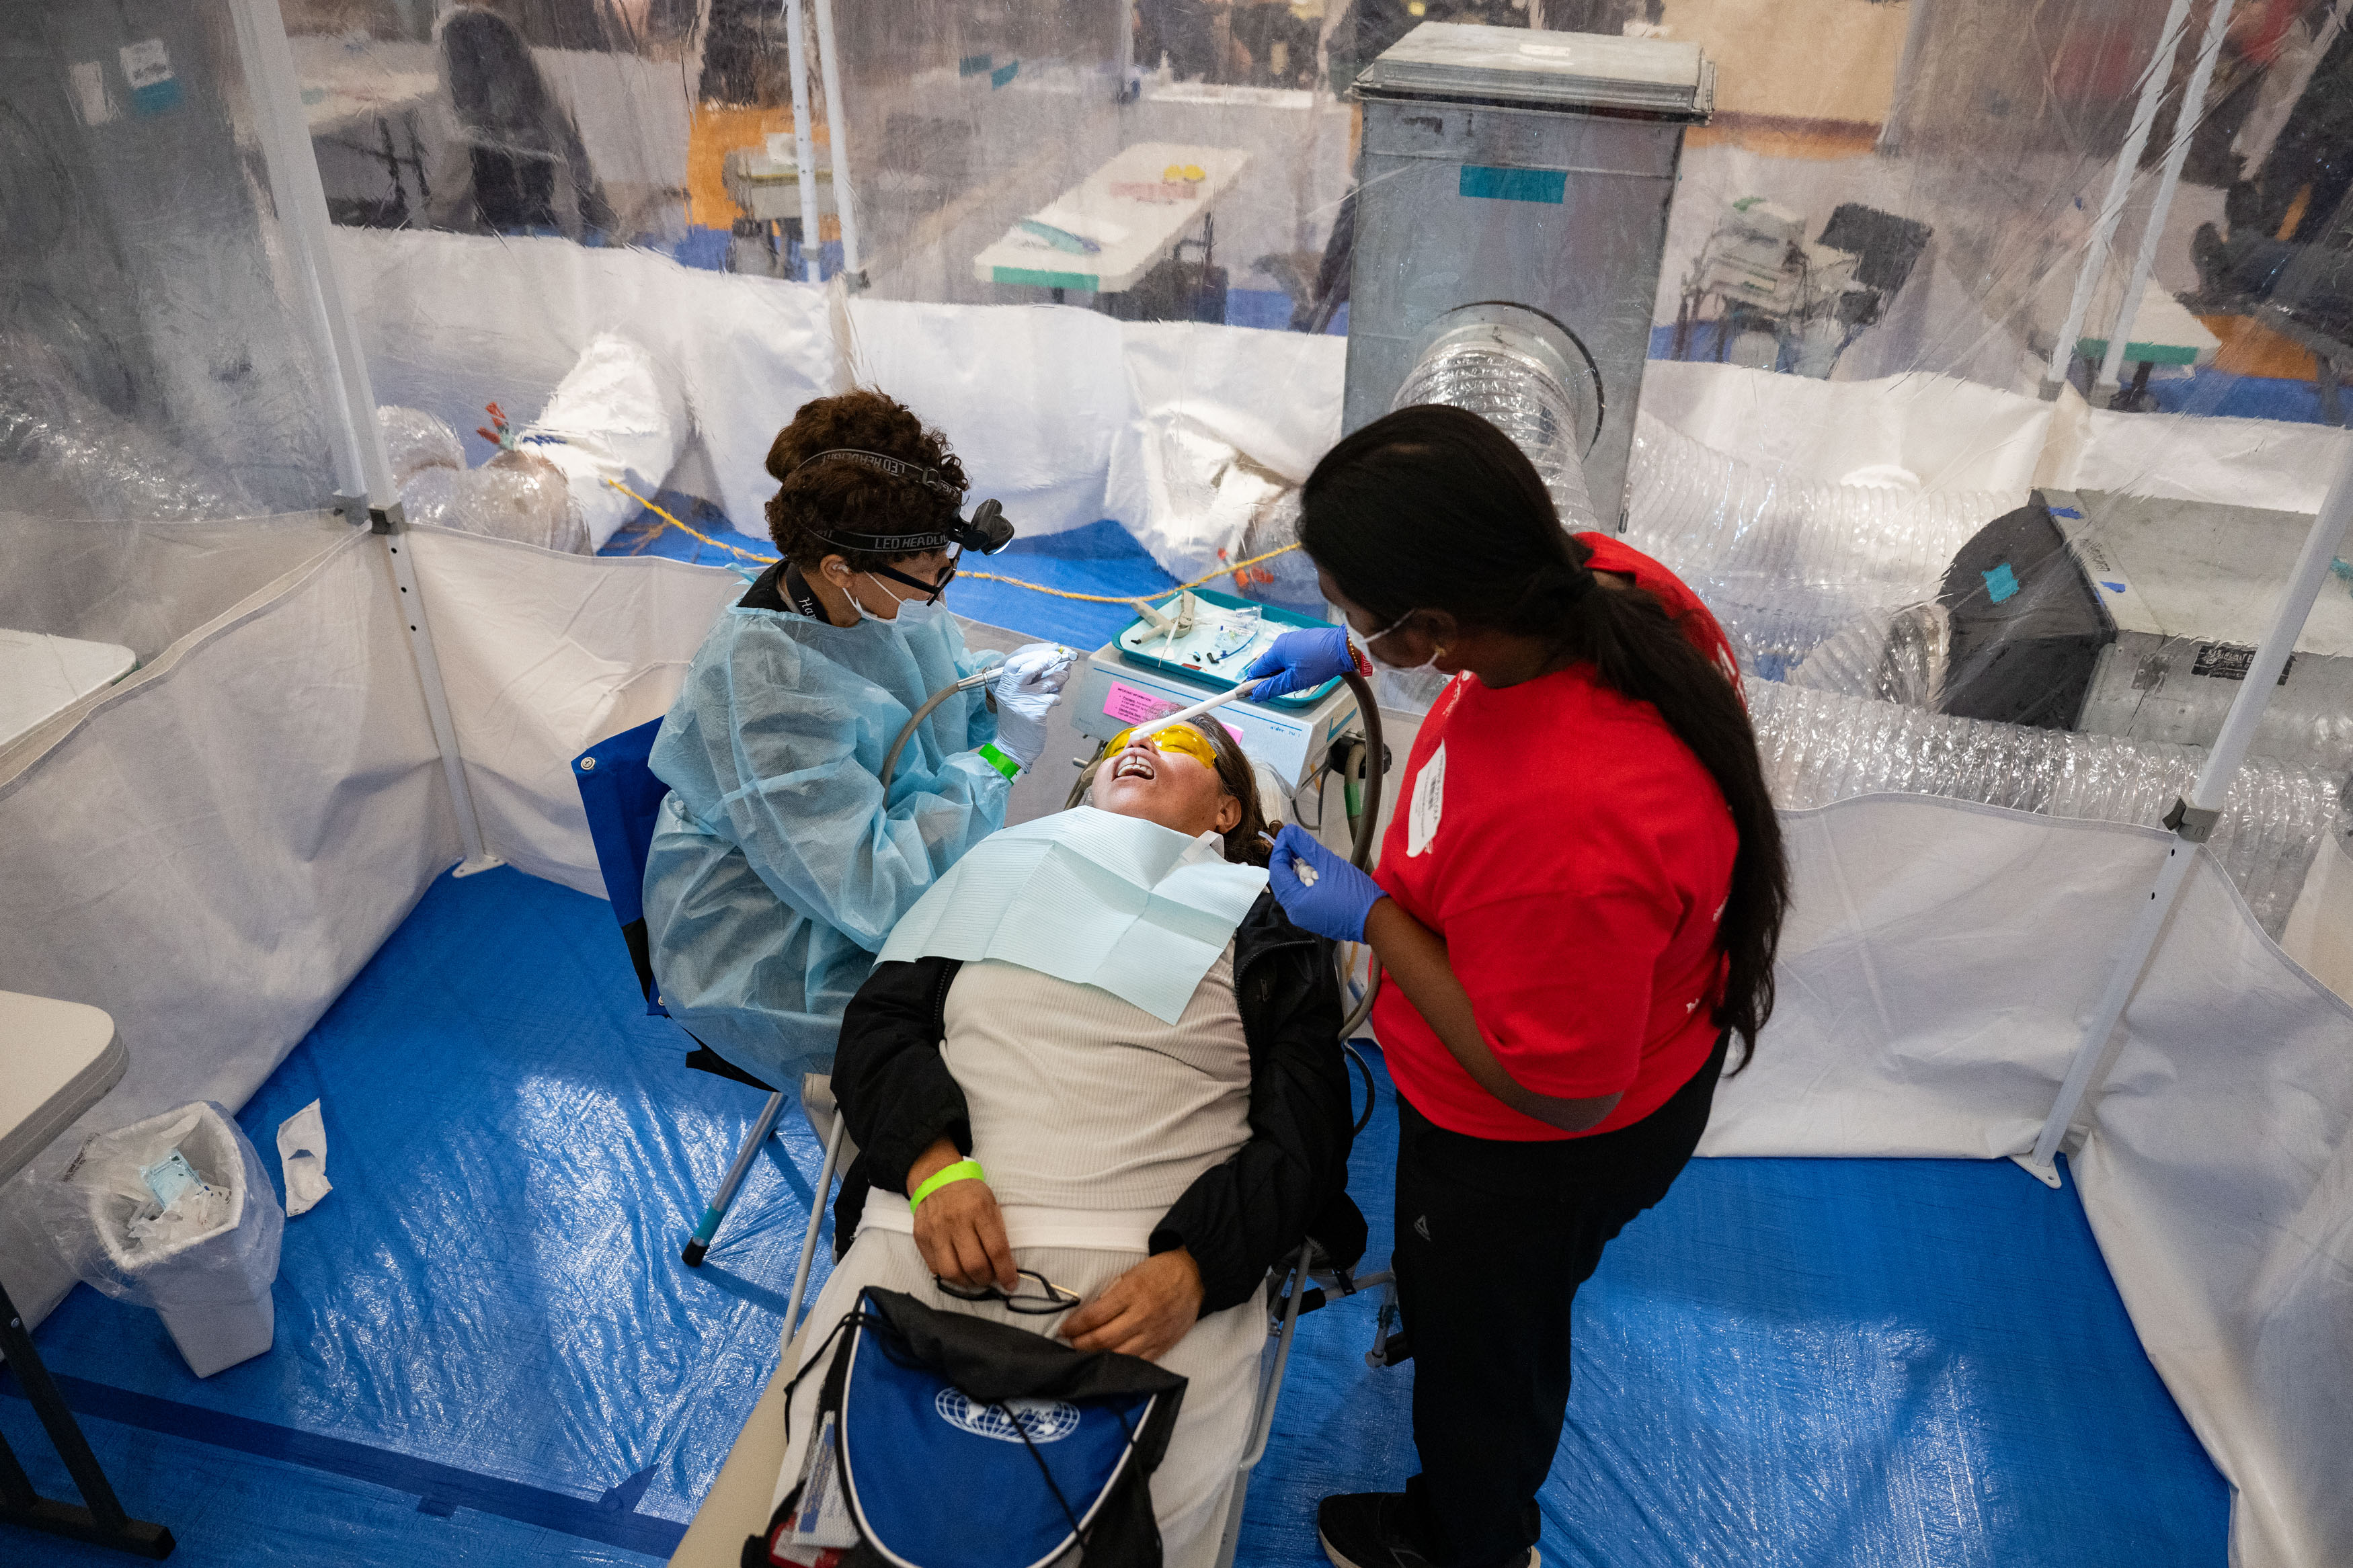
The dilemma, he said, is patients often need multiple teeth extracted and the volunteer dentists have only limited time for each patient. “We have to spread the love around because we have a busy schedule.”
Michel Boudreaux, an associate professor at the University of Maryland Department of Health Policy and Management, said the RAM clinic, about 5 miles from his campus, highlighted the growing difficulty people with and without health insurance face.
“Even in this suburban county there are a lot of uninsured people struggling with affordability and insured people struggling with high deductibles and copays,” he said.
Boudreaux called it “disheartening” that people felt they had to sleep in their cars overnight for care.
Having a government job with benefits was once seen as way of immunizing one’s family from rising health costs.
Cheromie Johnson, who works for the District of Columbia, said that recent dental work left her with a $12,000 bill.
She came to the clinic with her 6-year-old son, Cairo, to get eye exams. She was hoping they would each get a new pair of eyeglasses.
“This is very important, especially for him in school, and I drive, so we both need to see clearly,” Johnson said. She estimated the free vision care would save them more than $1,000.



When asked what this busy free clinic said about the state of U.S. healthcare, she said: “It’s poor, and it needs to be revamped. But we all know that.”
John Osborn, dental director for RAM, was taking a break on a balcony that overlooked the gymnasium, now peppered with treatment tents and mobile equipment that had transformed the space into something from the TV show M*A*S*H from decades ago. He was not surprised to see people showing up on a Saturday morning for care. Over the past 35 years, he’s seen similar scenes at RAM’s clinics across the country.
He only wished that some members of Congress would have come by to bear witness.
“It would have been nice for them to see what people have to do to get healthcare,” he said.
KFF Health News is a national newsroom that produces in-depth journalism about health issues and is one of the core operating programs at KFF—an independent source of health policy research, polling, and journalism. Learn more about KFF.
This article first appeared on KFF Health News and is republished here under a Creative Commons Attribution-NonCommercial-NoDerivatives 4.0 International License.
November 03, 2026RoseHealth - The New York Times, NYT > HealthNo commentsNovember 02, 2026RoseHealth - The New York Times, NYT > HealthNo commentsNovember 02, 2026RoseHealth - The New York Times, NYT > HealthNo commentsNovember 02, 2026RoseHealth News, KFF Health NewsNo commentsWhen U.S. Rep. David Valadao defended voting for a bill aimed at reducing Medicare spending by billions, the Republican noted his role in securing a key provision that will require some adult beneficiaries to work — a mandate he called “not an unreasonable ask.”
But the voters in his California Central Valley district, home to one of the most competitive House races in the nation, might get a pass from the Medicaid work rules in the One Big Beautiful Bill Act, which President Donald Trump signed into law last summer.
Starting in January, the law requires many nondisabled adults enrolled in Medicaid in 43 states and Washington, D.C., to work, volunteer, or go to school for at least 80 hours a month. But those who live in counties where a high number of people are out of work could get relief — one of several carve-outs in the law.
“Based on current numbers, every county in CA-22 would qualify for this exemption,” Valadao’s website says, referring to his district. “This waiver is important because it takes real-life situations into account, and if someone is trying to work but opportunities are limited, they won’t be required to.”
The congressman, who has said enrollees in Medicaid — the federal-state program covering the poor and disabled — should “put in a fair day’s work” if they can, declined an interview request. Valadao campaign spokesperson Paige Ash also declined to comment.

Valadao is among at least 21 Republican lawmakers running for reelection who voted for the 2025 GOP bill and represent counties that could qualify for a hardship exception, according to a KFF Health News analysis.
Roughly 6 in 10 residents in Valadao’s district are enrolled in Medi-Cal, the state’s Medicaid program. Researchers have estimated 60,000 more residents of his district could be without coverage by 2034 as a result of the One Big Beautiful Bill and the expiration last year of enhanced premium tax credits for Affordable Care Act insurance plans.
“It feels akin to an arsonist trying to take credit for helping put out a fire that they themselves ignited when all of this was avoidable pain from the outset,” said Miranda Yaver, an assistant professor of health policy and management at the University of Pittsburgh.
Valadao faces Democrat Randy Villegas in a district that was redrawn last year to lean more blue, and the two sides had each booked more than $16 million in advertising through Election Day, according to data compiled by AdImpact. Villegas and other Democratic challengers nationwide have made Republicans’ Medicaid vote a centerpiece of their campaigns, saying most enrollees already work, are disabled, or are caregiving.
The law allows states to apply for a short-term hardship exception for enrollees who live in counties where unemployment is at least 8%, or at least 1.5 times the national rate, whichever is lower. But it’s unclear how the Trump administration intends to implement that relief.
Some states have yet to submit their applications. Five Democratic-led states have asked the federal government to delay the work requirements, citing insufficient time to comply before the end of the year.
The press office for the federal Centers for Medicare & Medicaid Services, which is implementing the new law, told KFF Health News in an unsigned email that states may submit unemployment data from a “reliable” source, including figures from their own labor departments. But the agency hasn’t said exactly what time frame of unemployment data states should provide.

Unemployment data can be reported in a variety of ways. It can be from the most recent month, or a 3-, 6-, or 12-month average. That data will determine how many counties — and how many people — might qualify.
Using July 2026 unemployment rates, which are not adjusted for seasonal swings, 95 U.S. counties would qualify for the exception, according to an analysis by KFF, a health information nonprofit that includes KFF Health News. Using the 12-month average, the number of qualifying counties jumps to 120.
“Which data is used matters,” said Jennifer Tolbert, deputy director of KFF’s Program on Medicaid and the Uninsured. “I think there’s a lot still unknown.”
Sixty-four counties have high unemployment rates that will most likely qualify them no matter what data is used. The vast majority of the counties have a Republican representative. CMS declined to say how long exceptions would last or which states have applied. Indiana, Iowa, and Missouri do not plan to seek the hardship exception, according to KFF’s Medicaid work requirements tracker.
Some states are waiting for answers. California is among those that have asked to push back the start date. In September, the state asked CMS for permission to use state unemployment data that it says is timelier than federal data. State officials are waiting for a response, as well as for details about how long exemptions could be granted, said Griselda Melgoza, a spokesperson for the California Department of Health Care Services.
While blue states like California are seeking exceptions to help minimize the fallout of the new Medicaid rules, Yaver said any exceptions to the work rules could serve Republicans politically in the future.
“I think that exemptions and strategic burden reduction will ultimately undercut the accountability,” she said. “Because voters will just not really see the full reach of the law.”
KFF Health News is a national newsroom that produces in-depth journalism about health issues and is one of the core operating programs at KFF—an independent source of health policy research, polling, and journalism. Learn more about KFF.This article first appeared on KFF Health News and is republished here under a Creative Commons Attribution-NonCommercial-NoDerivatives 4.0 International License.
October 31, 2026RoseHealth - The New York Times, NYT > HealthNo commentsOctober 31, 2026RoseHealth - The New York Times, NYT > HealthNo commentsOctober 31, 2026RoseHealth - The New York Times, NYT > HealthNo commentsOctober 30, 2026RoseHealth News, KFF Health NewsNo commentsMillions of Medicare enrollees who buy stand-alone prescription drug plans will see their average monthly premiums rise by 50% in 2027, a new analysis finds.
But enrollees can avoid the average increase — from $34 a month to $51 — by switching to lower-cost plans during the program’s open enrollment period, which runs through Dec. 7.
Robert Travis Scott of Abingdon, Virginia, did just that in late October after he received a notice that his AARP-UnitedHealthcare Medicare drug plan premium would be increasing from $39.60 a month in 2026 to $121.90 in 2027. With just a little work checking prices online, Scott found a Humana plan for $19.30 with similar benefits.
“Yes, I am quite happy about that,” he said of the new plan he just found. He said he was stunned his existing plan was going up so much and worried that other seniors won’t shop for plans to save money. He estimates he saved himself about $1,000 for next year.
“With some plans increasing premiums substantially, the stakes are higher this year for people with Medicare stand-alone drug coverage if they sit on the sidelines during open enrollment,” said Juliette Cubanski, a vice president and the director of the Program on Medicare Policy at KFF, which conducted the analysis. KFF is a health information nonprofit that includes KFF Health News.
Rising drug costs are among the litany of affordability issues angering voters ahead of November’s midterm election. President Donald Trump, whose approval rating in some polls has dipped to the lowest level of his two terms in office, claims his administration has succeeded in negotiating lower prices from drug manufacturers.
“What we’re doing great with is pharmaceuticals, hundreds of billions,” Trump said at a campaign rally in Ohio on Oct. 28, ahead of the Nov. 3 midterms. “You should win just on this, everybody running. We have the lowest drug prices anywhere in the world. We went from the highest drug prices, we now have the lowest drug prices, favored nations, anywhere in the world.”
How much people actually pay for drugs varies widely, depending on what medicines individual patients need and their insurance coverage.
Medicare beneficiaries who get their drug coverage as part of private Medicare Advantage plans, which replace traditional Medicare coverage, will see much lower premium increases. The KFF analysis found these enrollees will pay an average of $9 for drugs as part of their overall monthly premium in 2027, or an increase of less than $2 per month.
More than half of Medicare beneficiaries are enrolled in Medicare Advantage health plans, which usually include a drug benefit, instead of the traditional program.
Nearly 25 million people are enrolled in Medicare stand-alone prescription drug plans, according to KFF. About 31 million get drug coverage through Medicare Advantage plans.
Premiums are just part of the higher costs Medicare enrollees are facing.
Most enrollees who buy a stand-alone drug plan or get drug benefits through Medicare Advantage plans will also have an annual deductible for drug coverage in 2027.
The average deductible in 2027 will be $643 for stand-alone plans, according to the KFF analysis, up from $540 in 2026. Drug deductibles will average $489 for those with Medicare Advantage plans, up from $360 in 2026.
In addition, most Medicare enrollees with drug coverage next year will have to pay coinsurance rather than copayments, the KFF analysis found. That can mean less predictable out-of-pocket costs because coinsurance requires paying a percentage of the cost of a drug, not a fixed amount.
One possible cause of the projected premium hikes is the Centers for Medicare & Medicaid Services’ decision in July to end early a three-year pilot program designed to keep down stand-alone premiums. The program paid subsidies to stand-alone plans in 2025 and 2026.
KFF said CMS’ decision to end that subsidy program after only two years could cause stand-alone premiums to rise in 2027.
CMS Administrator Mehmet Oz has called the subsidy program an insurance industry bailout.
KFF noted its analysis differs from CMS’ projection for a $1 increase in the national average premium, from $35 to $36, based on September 2026 enrollment. It said that CMS did not explain its calculation methods and that it’s possible CMS assumed people would switch to lower-cost plans.
CMS did not immediately respond to a request for comment on the KFF findings.
About 10.4 million Medicare enrollees, or 76% of enrollees in stand-alone drug plans who don’t get low-income subsidies, will pay a higher monthly premium in 2027 if they stick with the same plan, KFF found.
This includes 4.1 million enrollees who are currently in a zero-premium plan. They’ll automatically pay more in 2027, because there will be no zero-premium plans available, the KFF analysis found.
KFF Health News is a national newsroom that produces in-depth journalism about health issues and is one of the core operating programs at KFF—an independent source of health policy research, polling, and journalism. Learn more about KFF.This article first appeared on KFF Health News and is republished here under a Creative Commons Attribution-NonCommercial-NoDerivatives 4.0 International License.
October 30, 2026RoseHealth News, KFF Health NewsNo commentsChris McQueen finished treatment for leukemia a year and a half ago, but the ads for fake cures never stopped.
Juice cleanses to cure cancer, “natural” cancer treatments, clinics in Mexico promising full recovery with little chemotherapy — all appeared on McQueen’s mobile phone during routine oncologist visits and monthly bloodwork.
McQueen and others have taken to social media to vent about companies known as data brokers tracking their whereabouts via their smartphones’ location data, connecting it with other data gathered about them, and then drawing inferences about their health struggles to sell to companies hawking unproven treatments.
“It makes me feel sick to my stomach,” said McQueen, who lives in San Diego and fears some patients are putting themselves at risk, potentially fatally, if they try such untested treatments instead of following their oncologists’ advice.
More than 92% of patients in a 2022 American Medical Association survey said they believed their health data should not be available for purchase. But many people might not realize that when they are sitting in a hospital, an abortion clinic, or an Alcoholics Anonymous meeting in a church basement, the location data emitted from their mobile phones isn’t covered by the Health Insurance Portability and Accountability Act, better known as HIPAA, which protects patient privacy.
That worries Eric Ellsworth, director of health policy and innovation at the Center for the Study of Services, a nonprofit focused on delivering consumers reliable information on local medical services and healthcare professionals.
“Data brokers typically are just hoovering up data from the open web and then buying it from anybody,” he said.
The U.S. government has begun to penalize some companies that track Americans when they visit health facilities and places of worship. But privacy and legal experts don’t think actions against a few companies will stop an entire industry built on scooping up Americans’ private data. They’re calling on more states or Congress to ban advertisers from tracking Americans’ locations via their phones.
But progress has been fitful. California Gov. Gavin Newsom, a Democrat, on Sept. 27 vetoed a bill that would have blocked the sale and sharing of location and other sensitive personal data, saying it went “a step too far.” And a recent study from Stanford University showed that only 9% of data brokers are adhering to an existing California privacy law that gives consumers the right to delete their data, correct personal information, and learn what personal records the business is selling.
In January, Consumer Reports released model legislation giving state lawmakers a framework to ban or limit the sale of geolocation data, which uses GPS to identify a person’s movements in real time. Connecticut, Delaware, Maryland, New Jersey, Oregon, and Virginia have already banned the sale of precise geolocation data. But digital advertisers have also lobbied states to block such proposed limits.
The Money Behind Data Sales
Data brokers and advertisers argue that location data itself is not sensitive data, said F. Mario Trujillo, senior staff attorney at the Electronic Frontier Foundation, a nonprofit that champions user privacy. “But location data is sensitive. It’s the comprehensive collection of location data that reveals sensitive things.”
Advertising trade groups say that targeted advertising saves consumers time and lowers the cost of searching for products, while also allowing websites and apps to offer digital services without paywalls or subscriptions.
“A national privacy law should protect consumers from harmful or unexpected uses of data without preventing businesses from providing the services consumers request and expect,” said Jim Potter, executive director of 4As Health, a subsidiary of the American Association of Advertising Agencies. “That balance is especially important in advertising, which is not merely a business model but a key part of the modern economy.”
The U.S. government has begun to look into industry practices. In August, the Federal Trade Commission warned retailers about using private consumer data to increase prices.
In May, the agency also placed limits on a data broker that the agency began investigating in 2022. That settlement prohibits Idaho-based data broker Kochava and a subsidiary from “selling, sharing or disclosing sensitive location data without consumer consent” following allegations that the companies “sold location data from hundreds of millions of mobile devices” that could be used to trace the movements of people when they visited hospitals, churches, abortion clinics, and other sensitive locations.
Kochava did not respond to requests for comment.
While privacy advocates have welcomed the government actions, they pointed out that the terms of individual settlements don’t apply to other companies, because settlements aren’t laws or regulations.
Meanwhile, digital advertising has become a major source of profits for big tech companies, which often offer consumers services such as apps, email, and cloud storage in exchange for monetizing personal data. A 2024 report by Federal Reserve Bank of St. Louis economists on the economic implications of digital advertising showed that the profit margins for three of the four biggest tech firms — Google parent Alphabet, Facebook parent Meta, and Microsoft — were at least twice as large as the services sector average.
Other studies have shown that once data brokers build their collection systems, they face minimal additional costs to sell the same data repeatedly, including to AI companies. And their reach is wide: A 2019 study found that data brokers had data tied to more than 90% of Facebook accounts in the United States. And a 2020 report by the Electronic Frontier Foundation said Google shared sensitive user data — including geolocation, device IDs, identifying cookies, and browsing history — with potentially hundreds of digital advertising companies.
Neither Google nor Meta responded to requests for comment. Microsoft has supported a national privacy law in the U.S., similar to one in the European Union. Microsoft spokesperson Paige Fisher said the company “has long believed that people should not have to give up their privacy simply because they use modern technology.”
‘Pretty Big Attack Surface’
The San Diego-based Privacy Rights Clearinghouse and the Electronic Frontier Foundation identified 750 data brokers operating in the U.S. as of last year. But they said many have not registered with state governments and may not offer easy opt-out forms or the ability for people to check the accuracy of their files, as one can for a credit report.
“We’re seeing a lot of scary stories,” said Matt Schwartz, a policy analyst at Consumer Reports who focuses on privacy.
Consumer Reports reported in September that when it had volunteers look at files companies had built about them, the information was often riddled with errors. One person’s report “showed four different ages, listed him as both male and female, predicted three markedly different incomes, and listed his jobs as ‘farmer,’ ‘homemaker,’ and a ‘self-employed white collar’” though he was none of those.
The data brokers create marketing lists that categorize consumers based on location data collected from their devices, Schwartz said. That could include whether they have visited reproductive health facilities, taken part in protests, or supported a particular political party by attending a rally.
He’s also worried about the risk of data breaches.
“The fact that we have an entirely unregulated space where anyone can buy and sell this information means there are hundreds of data brokers that are collecting this information,” Schwartz said. “That’s a pretty big attack surface.”
Opting Out
One way companies are attempting to address privacy concerns is by asking internet users to “opt in” to sharing their geolocation and health data. But Schwartz said opt-ins often contain verbiage allowing for the unlimited use, sharing, and sale of consumers’ location and health data. He said it presents consumers with an awkward choice — opt in and share sensitive data, or be blocked from using the website or app.
The other problem is that even when sensitive locations are stripped from a customer’s profile, data brokers and advertisers can still track a person’s route right up to the boundary of a sensitive zone and pick it up immediately upon departure, making it easy to infer the destination, the Electronic Frontier Foundation said in an August policy paper.
“If you’re tracking an individual, you track them from their home to their work, and then you track them going to a medical facility,” EFF’s Trujillo said, describing the sensitive locations as essentially blackout windows on the map. “There would still be this assumption that you’re entering that medical facility.”
To increase privacy on mobile phones in the absence of federal laws, Trujillo recommends people limit which apps track their location data and disable ad tracking on their phones. It is also possible to turn off location data or put phones in airplane mode before heading to sensitive locations.
While policymakers debate new privacy laws, doctors such as Julien Cavanagh say they are left to fix the mess that targeted online ads for fake cures create for patients’ health. Cavanagh, a neurologist in Atlanta, said he now asks patients whether they are taking supplements bought online when they show up with unexplained neurological symptoms.
“Some of these sham treatments can be toxic, cause vitamin or micronutrient deficiencies, or counteract the action of their prescribed medications,” he said. “The targeted ads are very common and insensitive.”
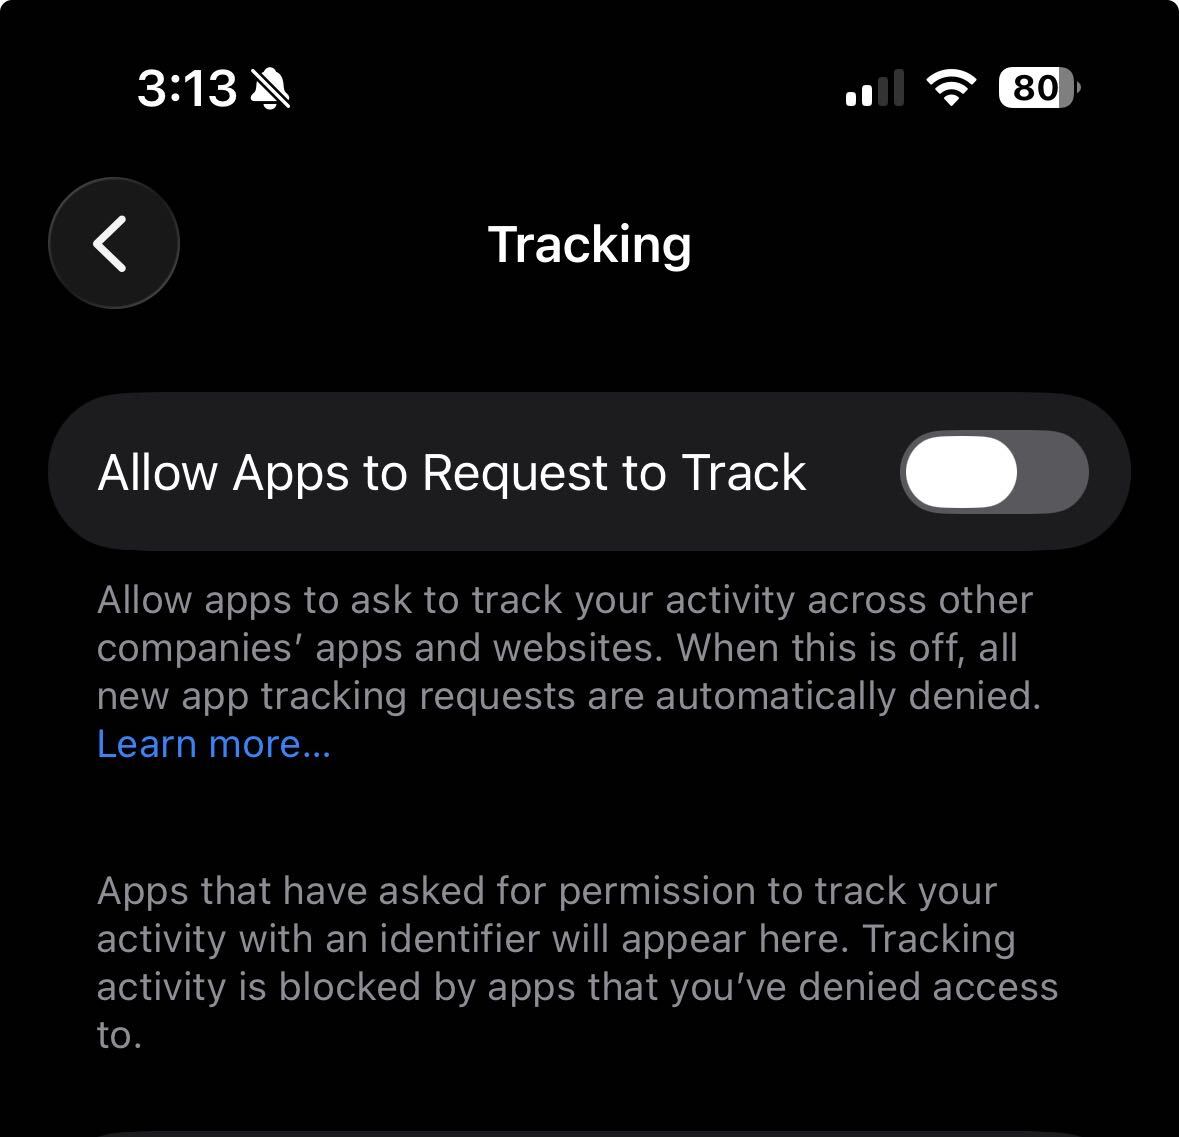
How To Stop Your Phone From Tracking Your Location in Healthcare Settings
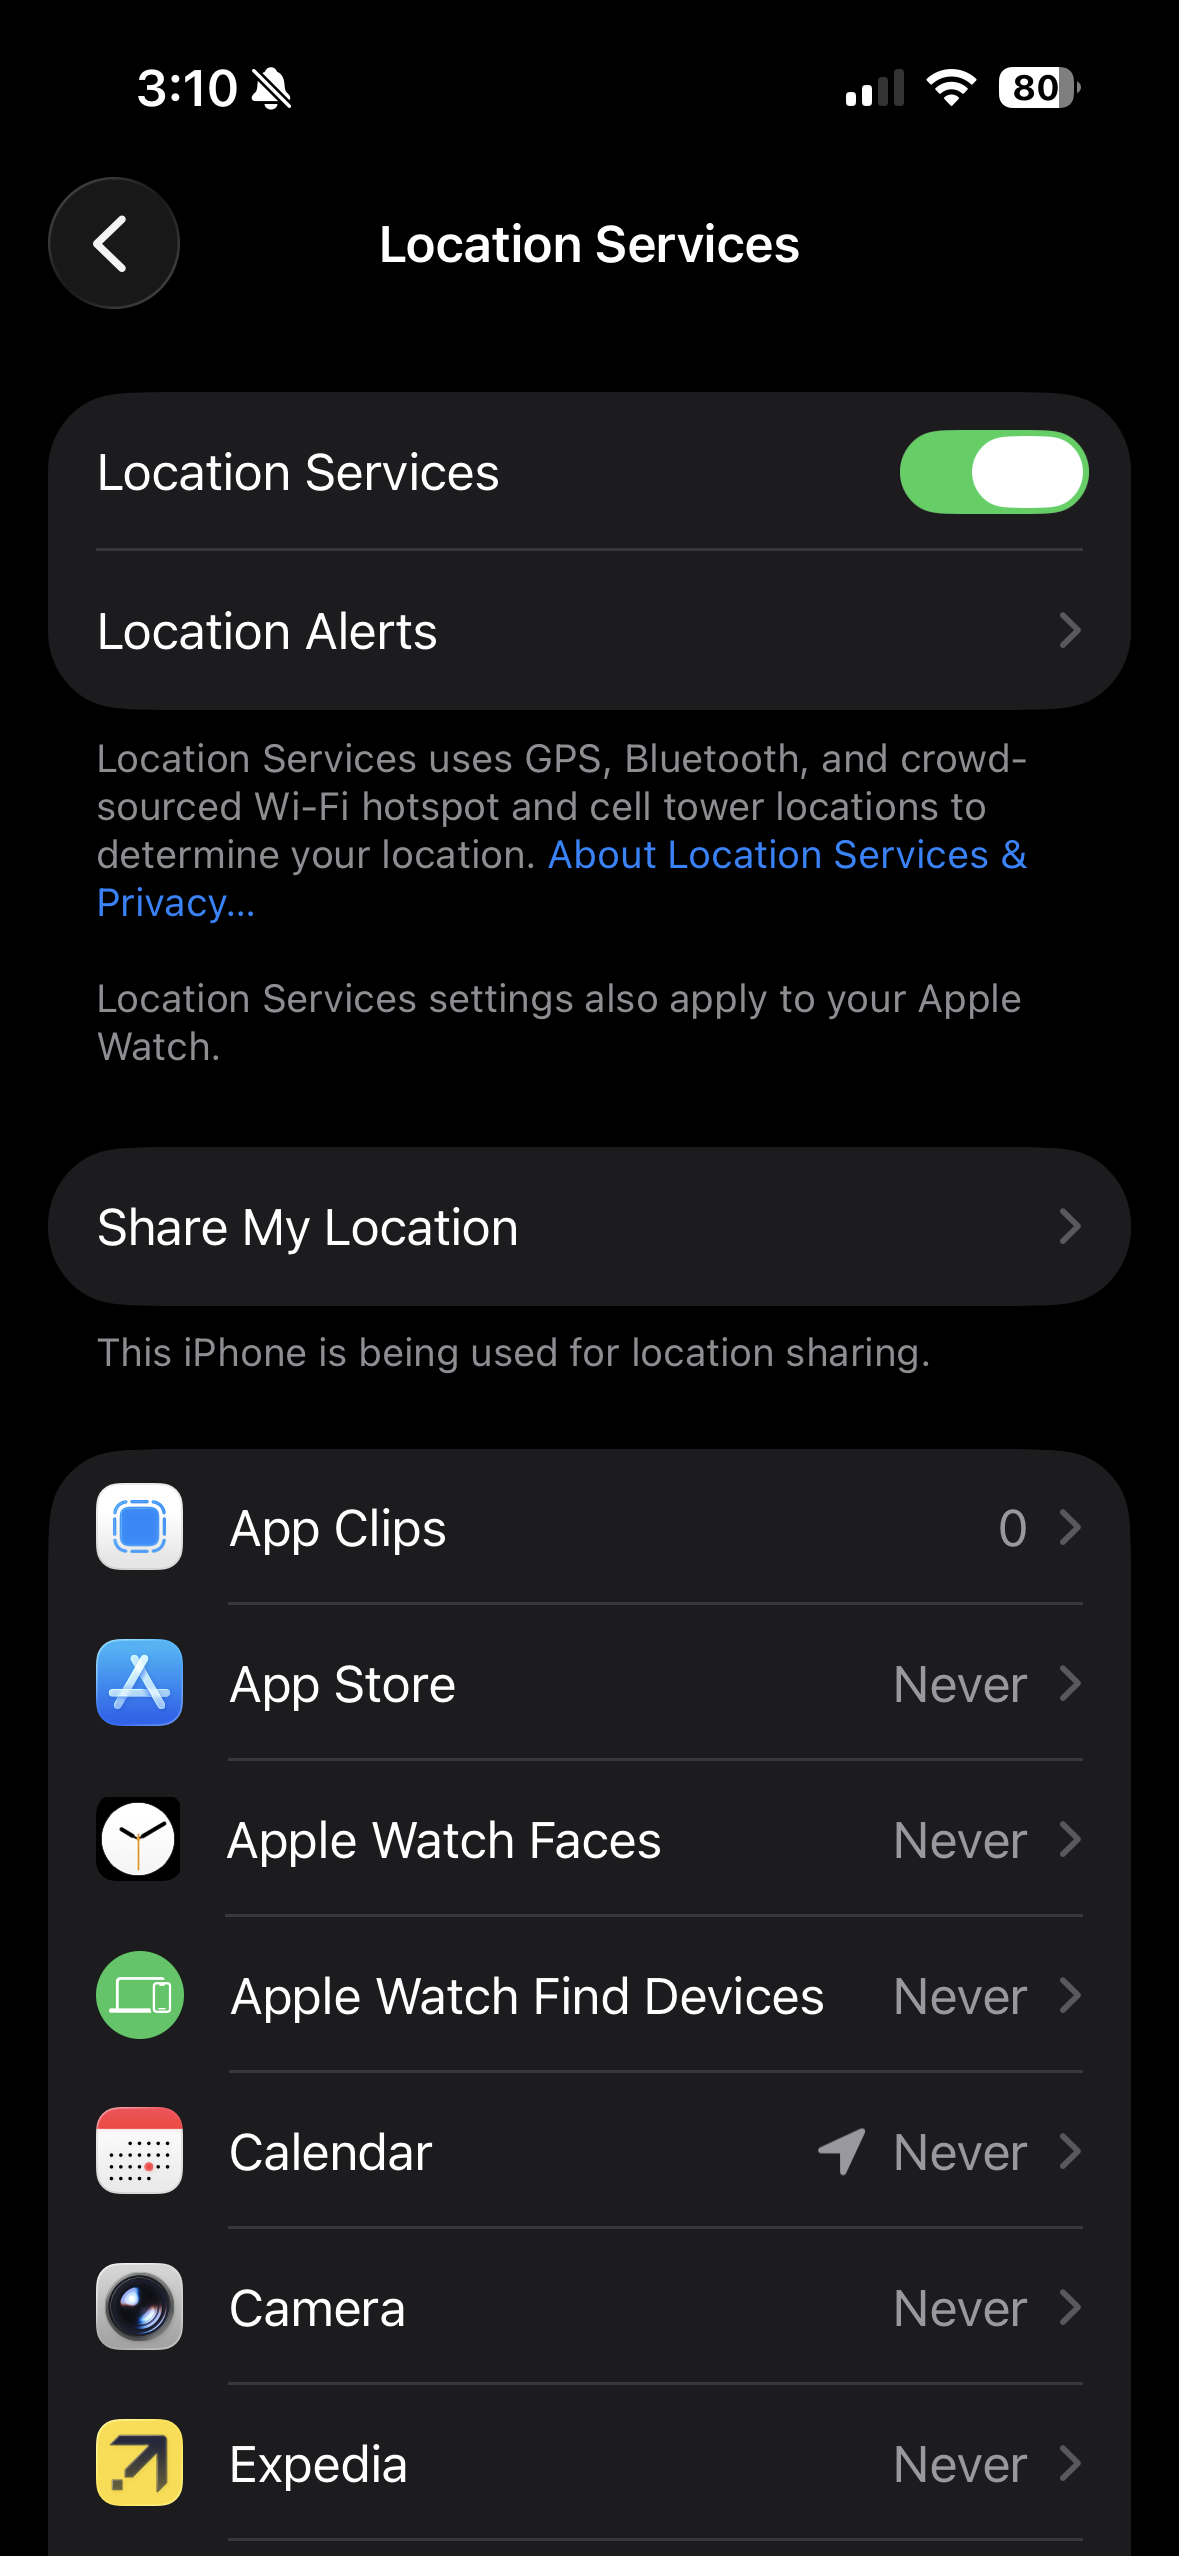
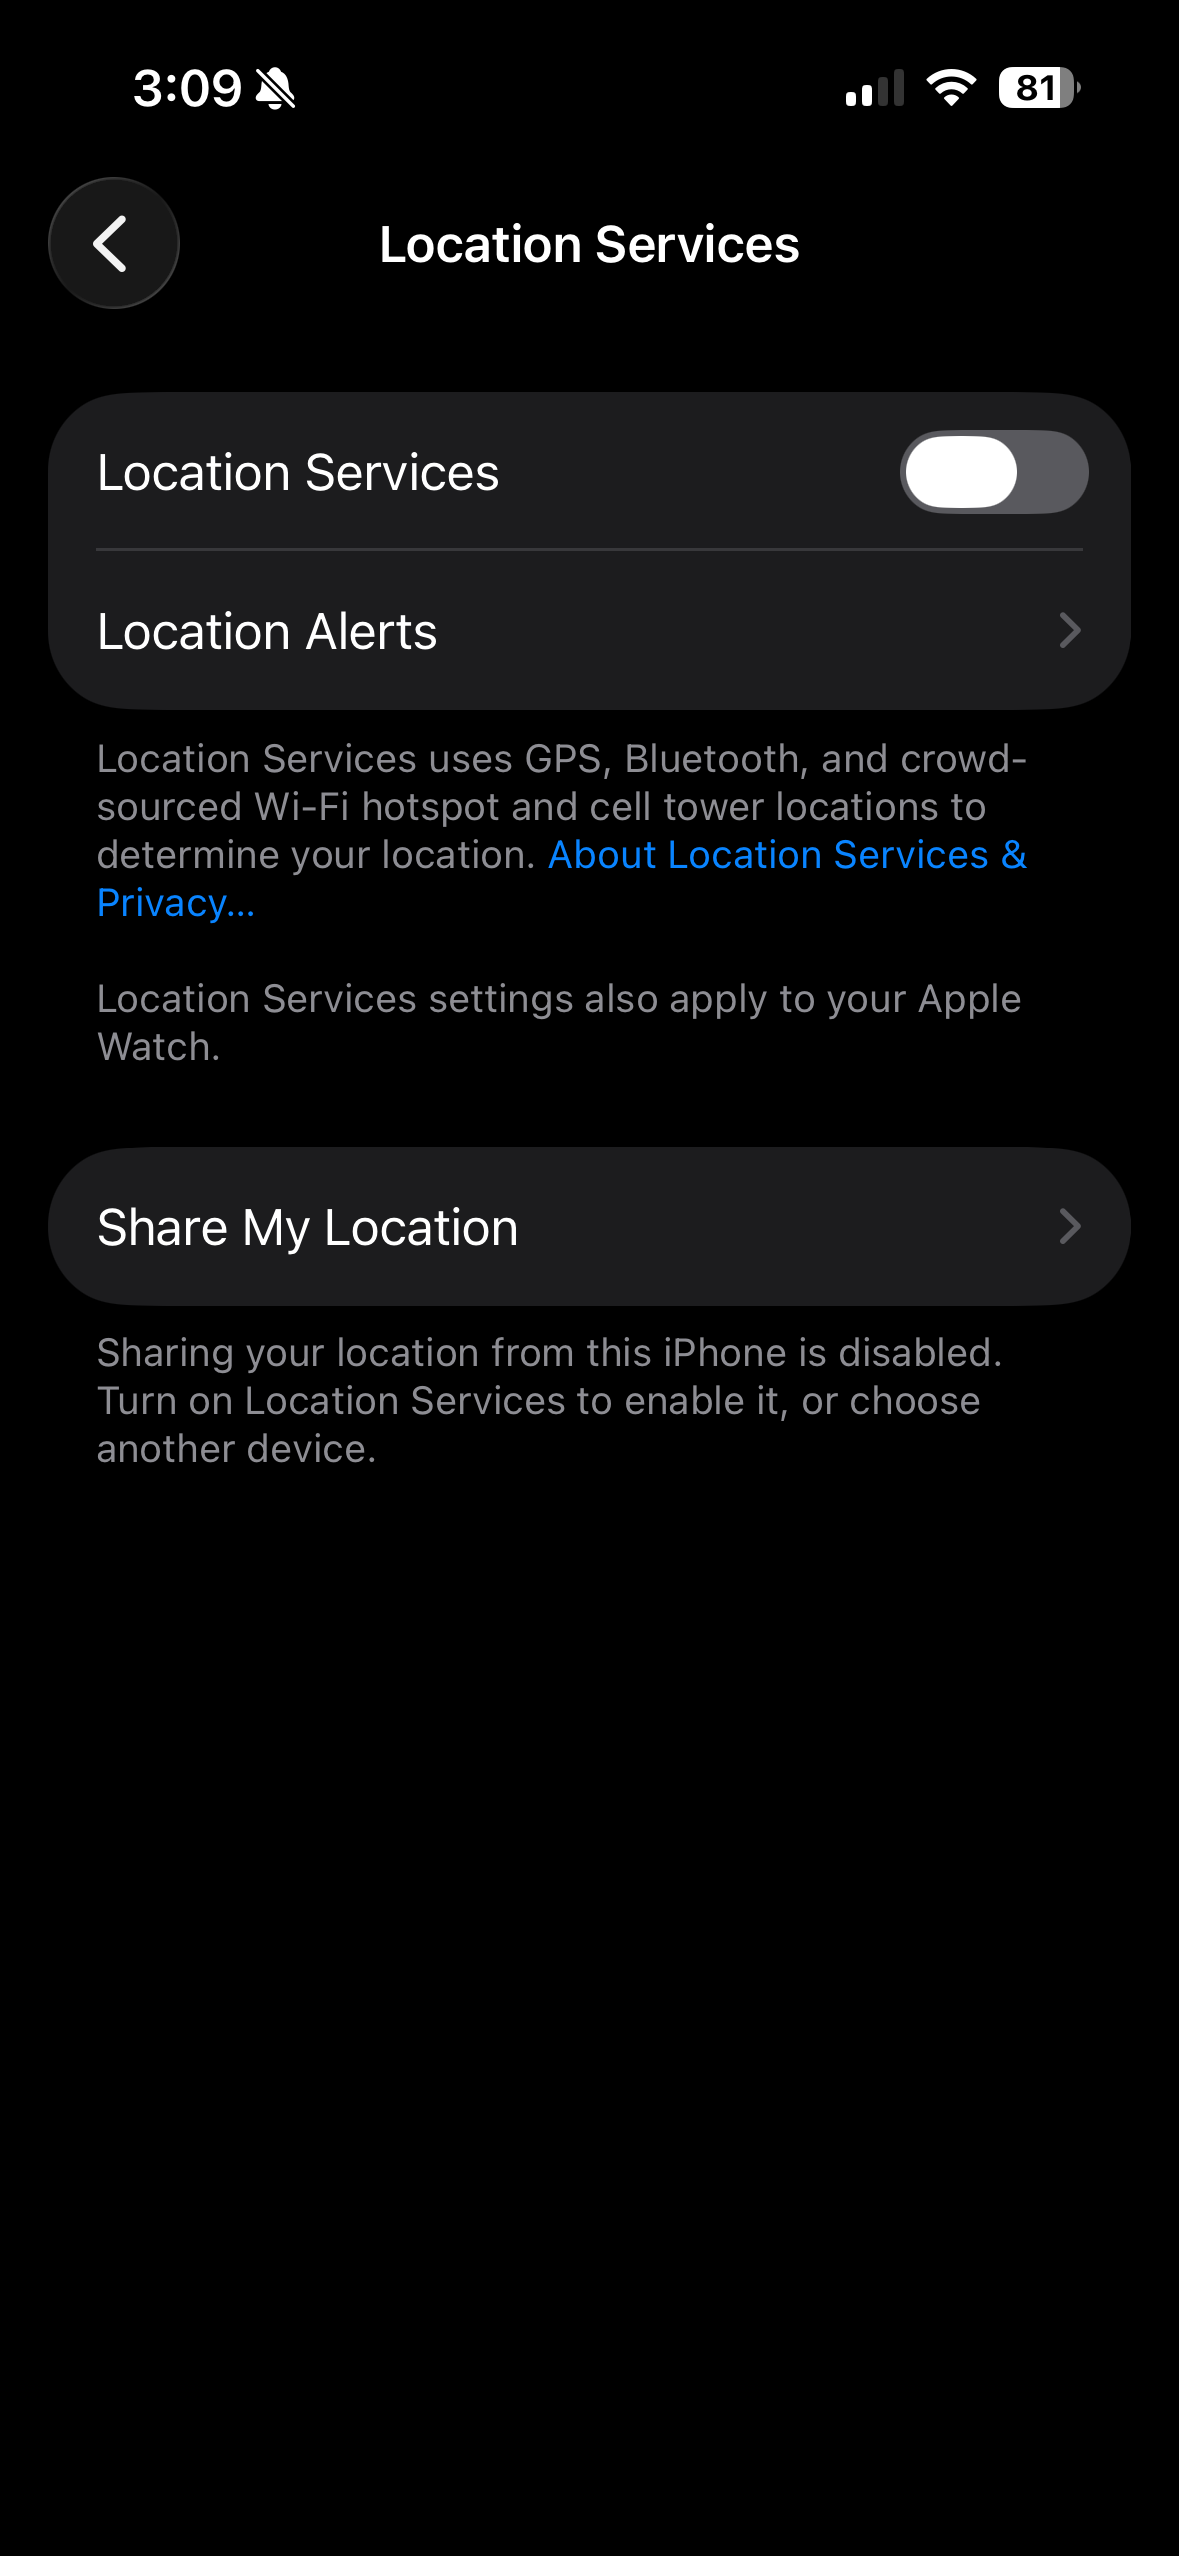
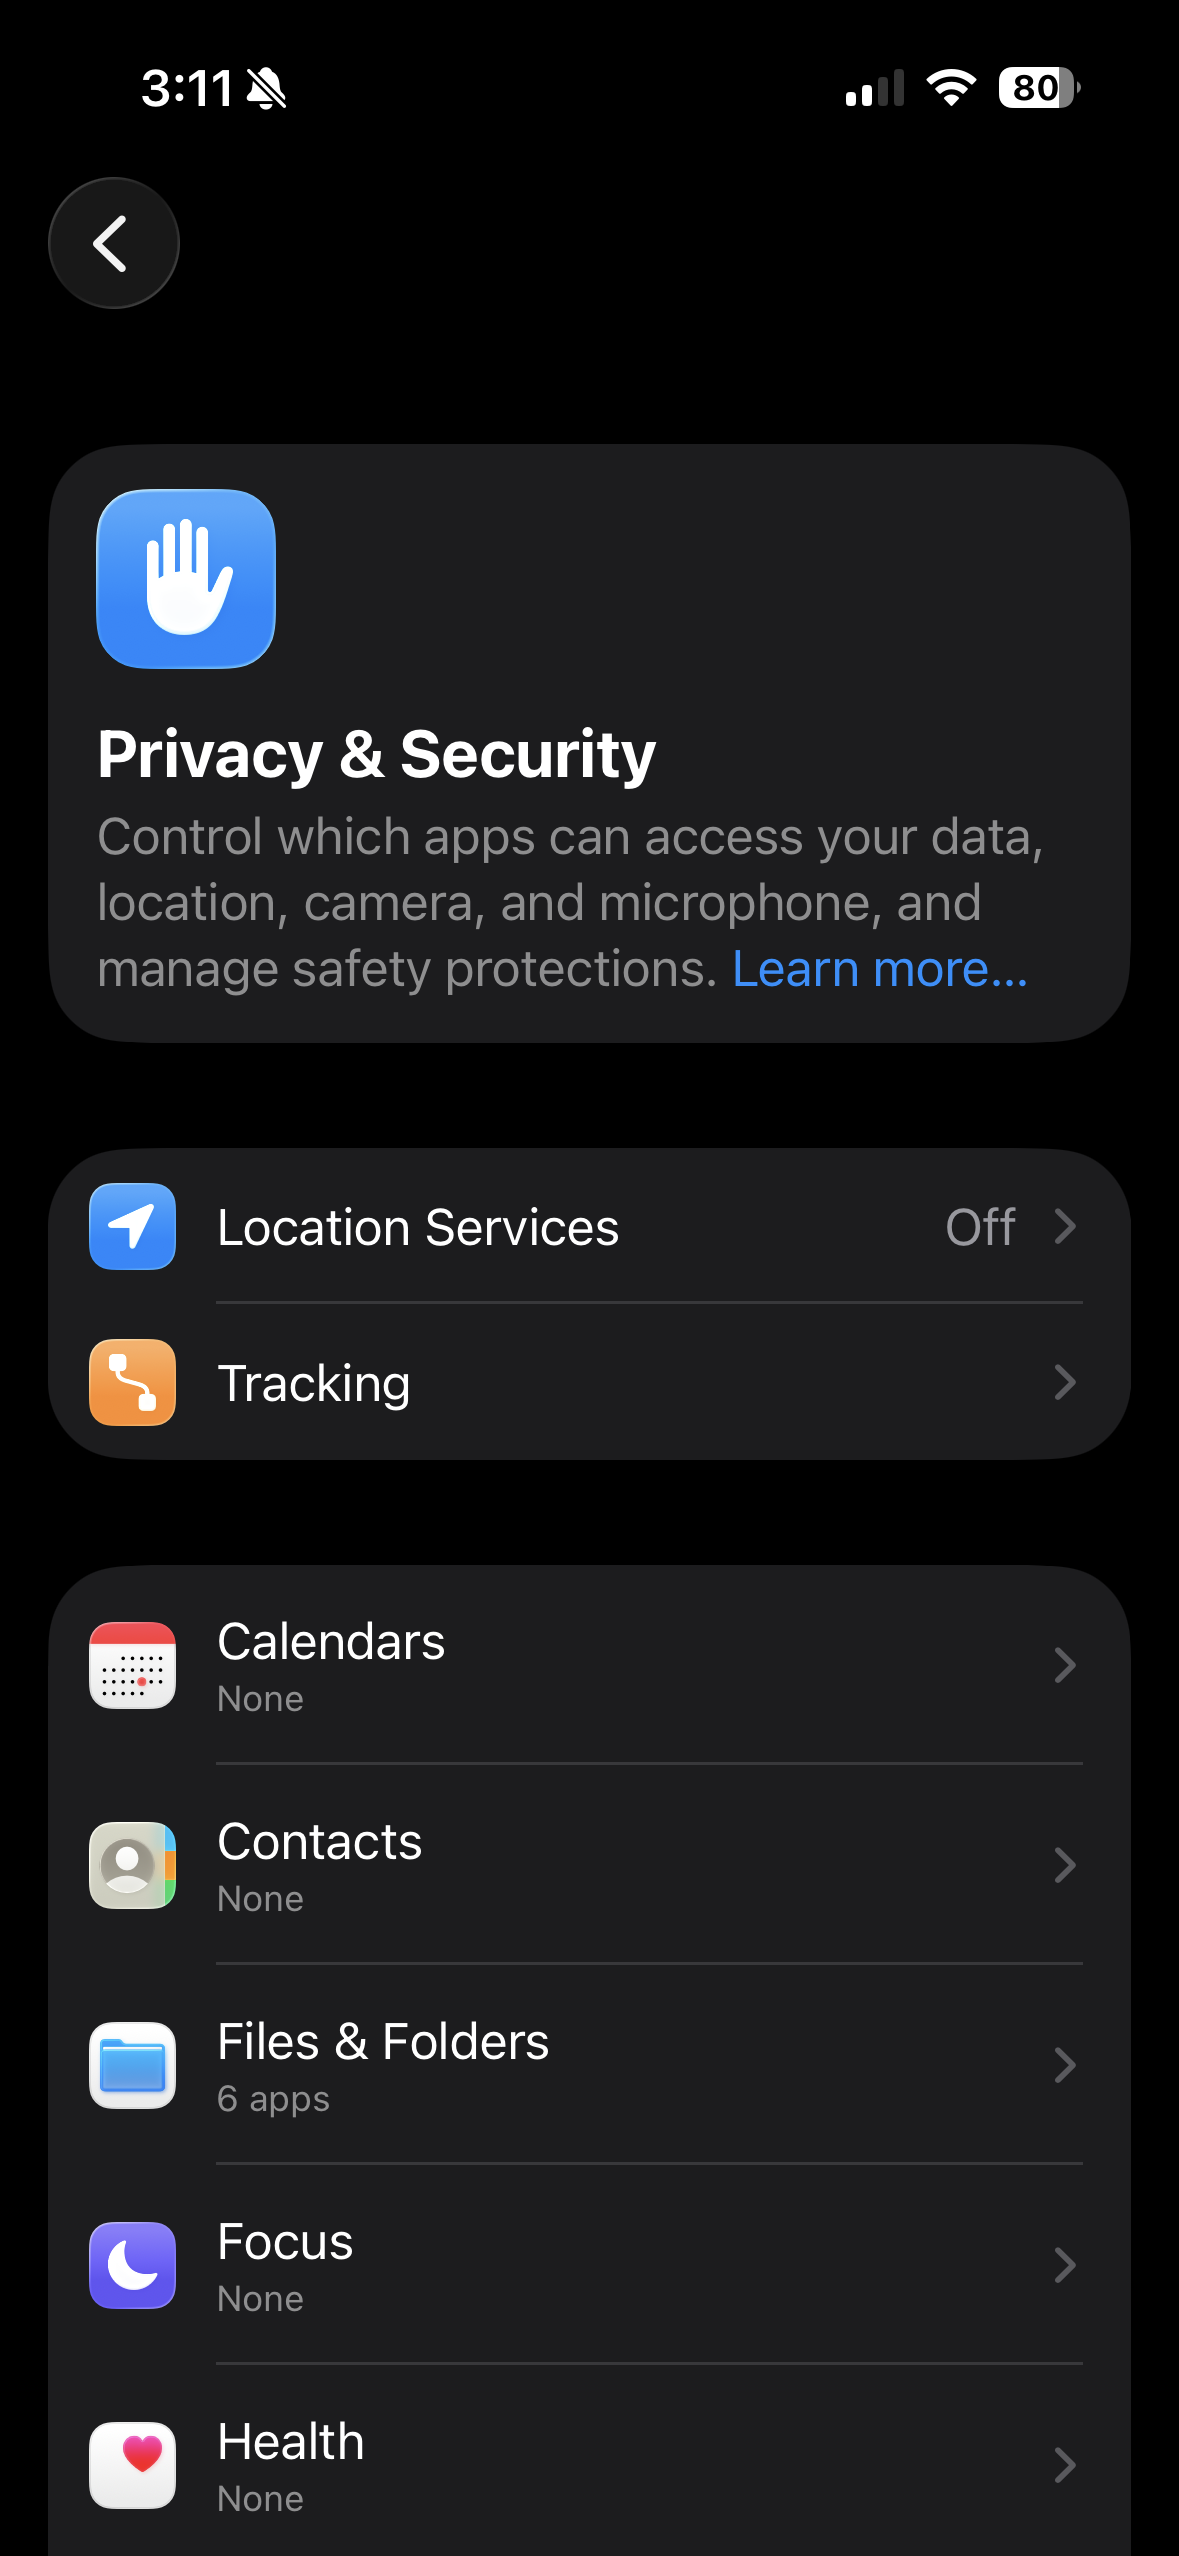
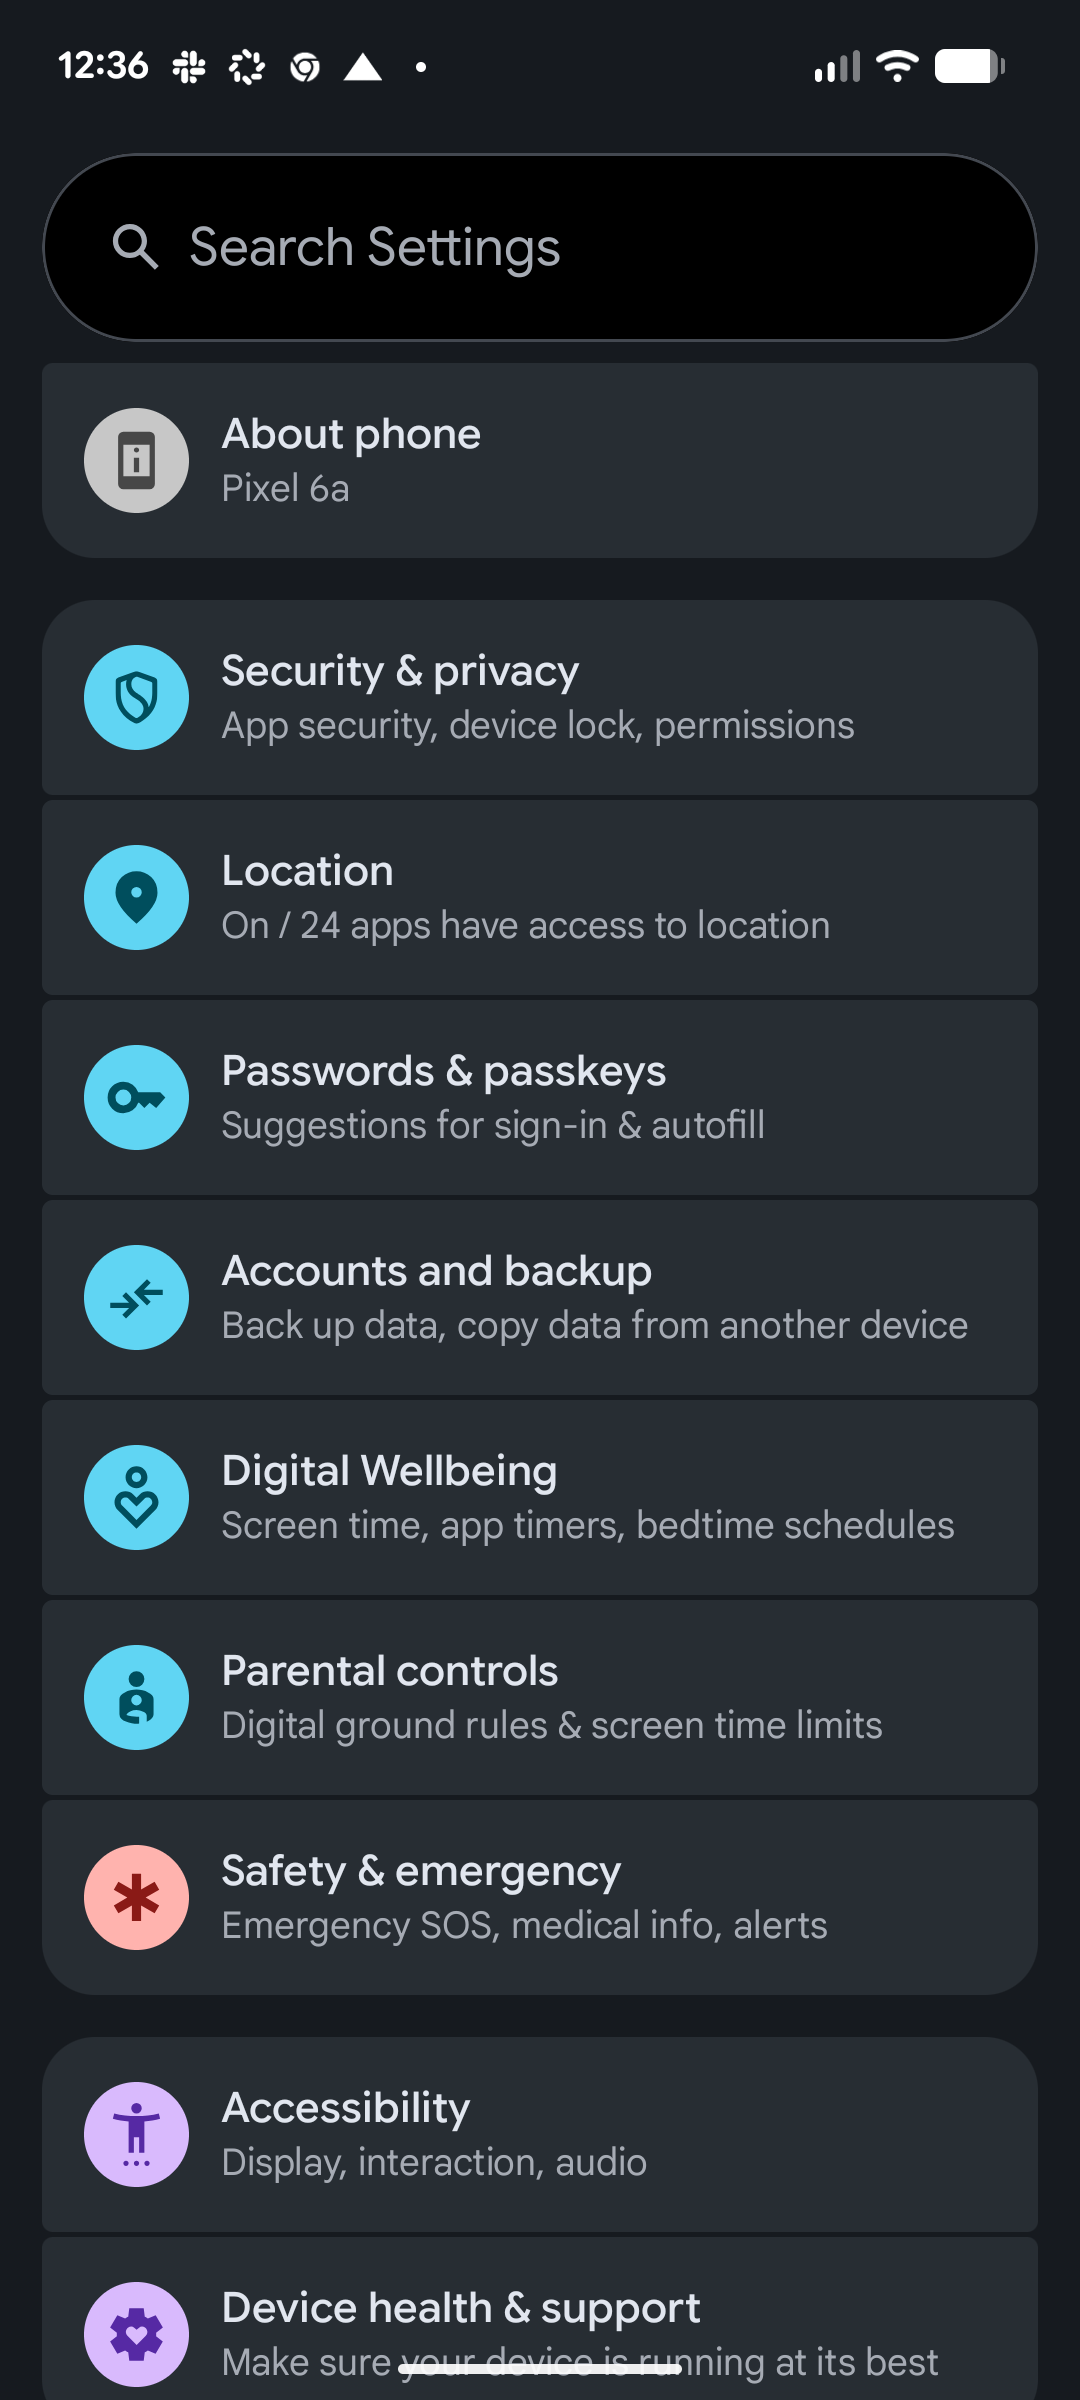
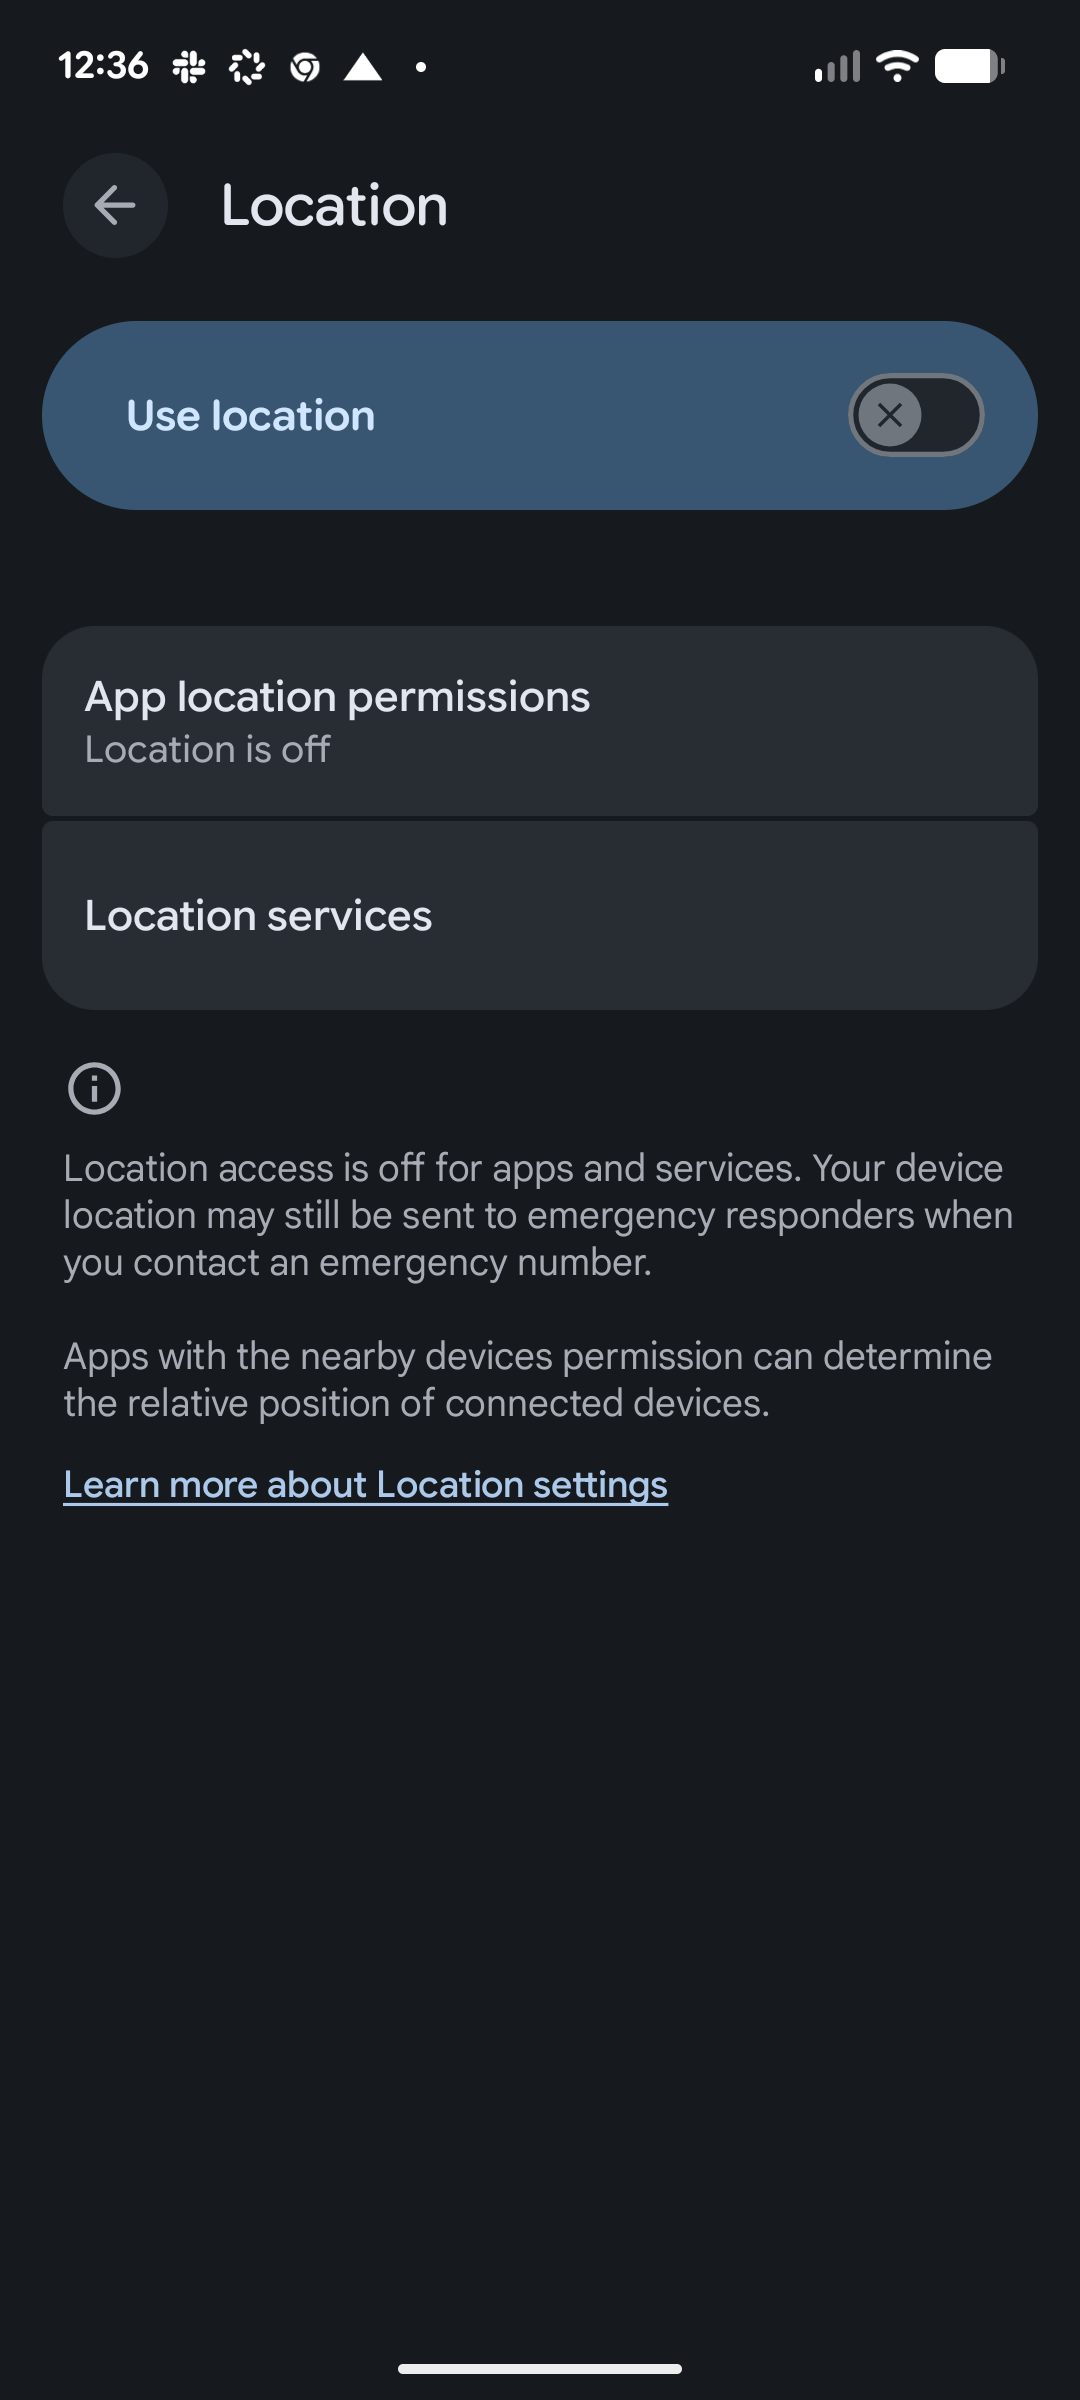
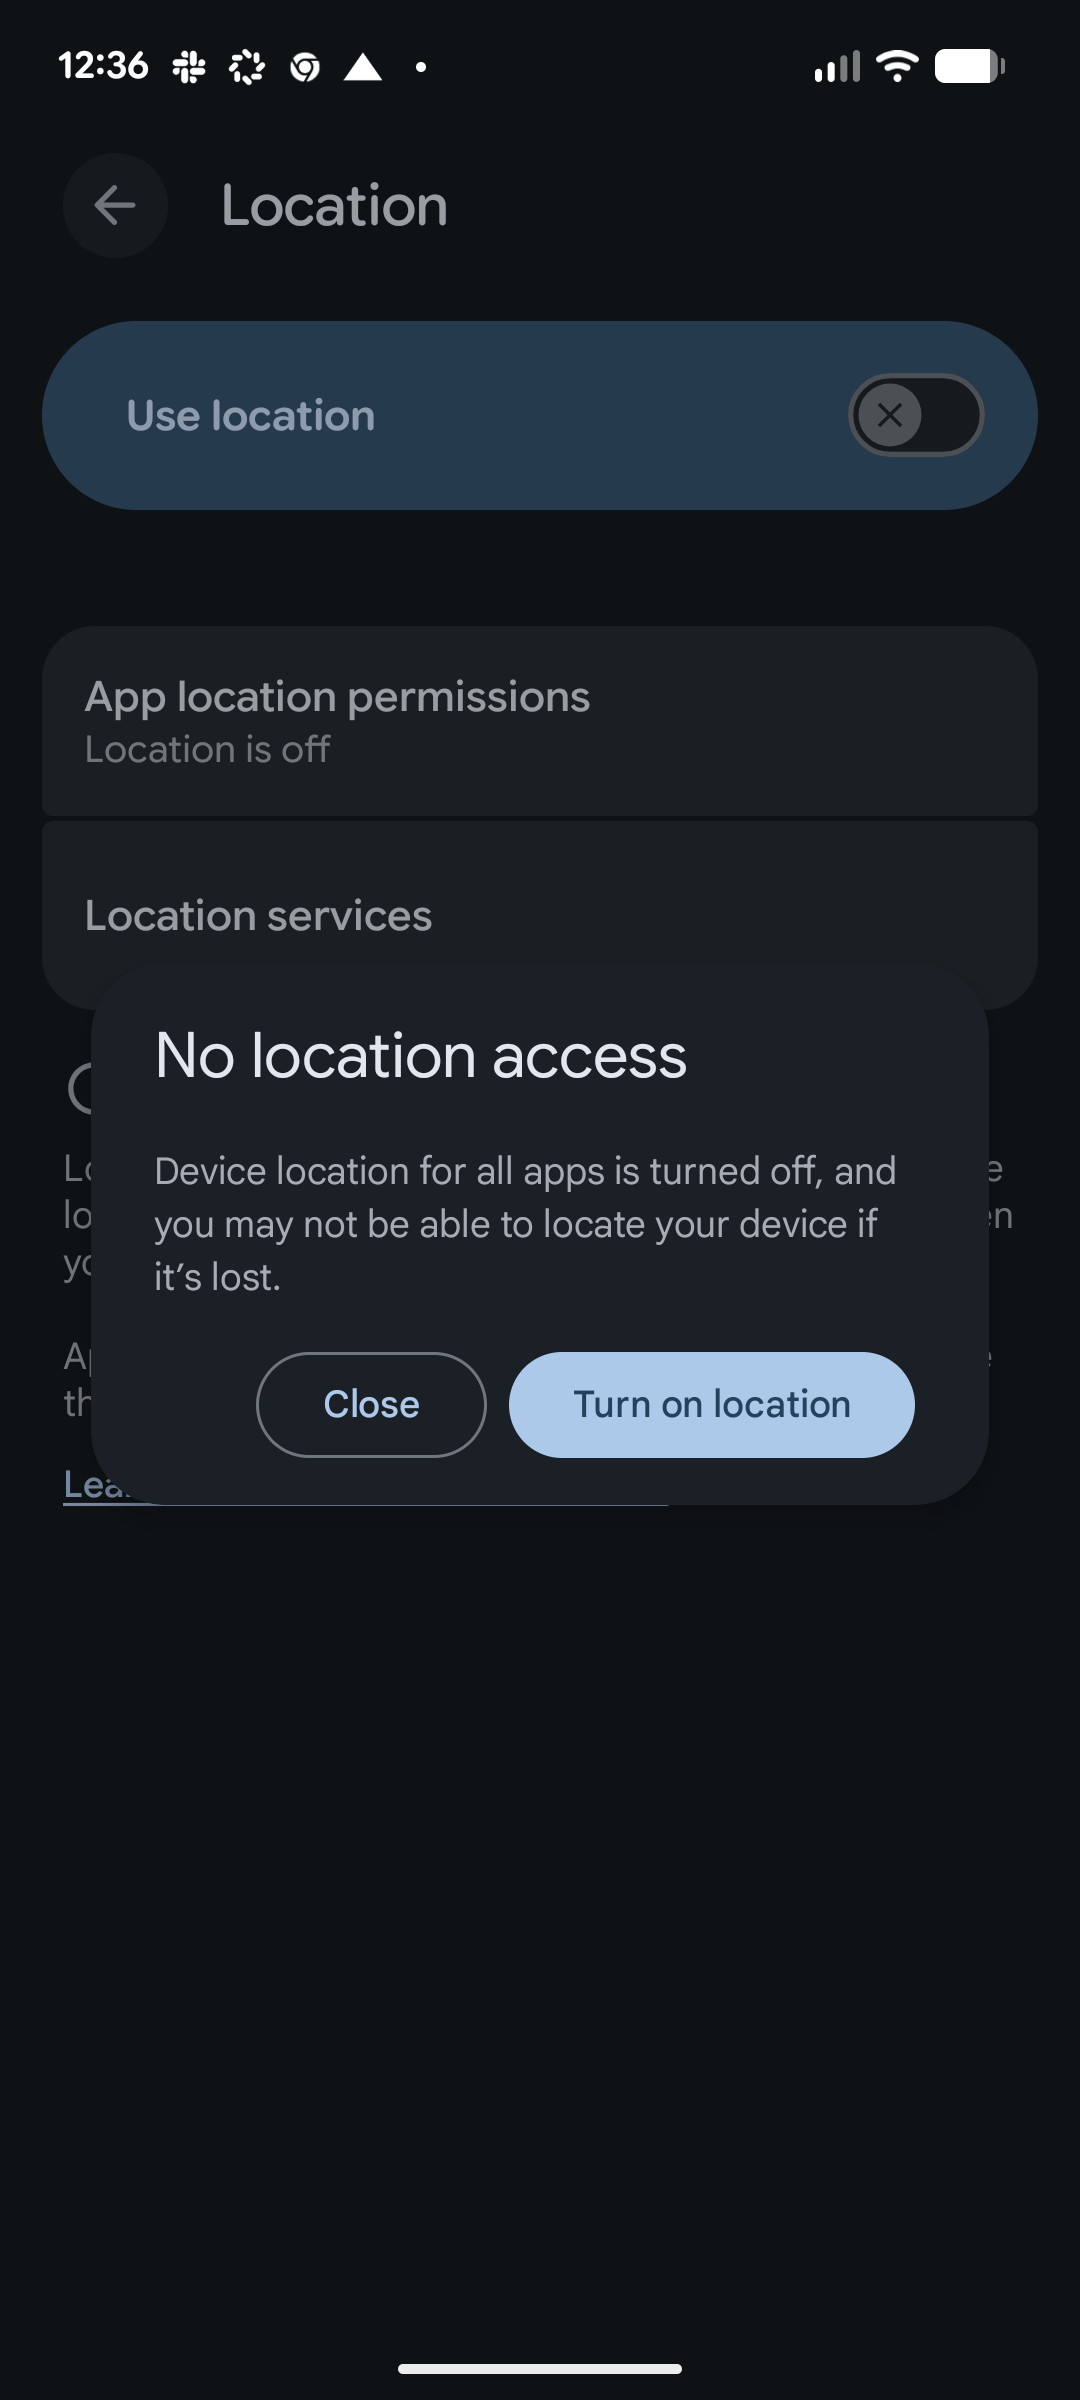
At least 20 states allow their residents to demand that data brokers delete their personal data, but typically consumers must file requests with individual data brokers. California has a centralized portal for requesting such opt-outs, at privacy.ca.gov/drop/. People also can change their mobile device settings to prevent tracking:
On an iPhone:
To turn off location tracking:
To stop data brokers from tracking you:
On Android:
To turn off location tracking:
To stop data brokers from tracking you:
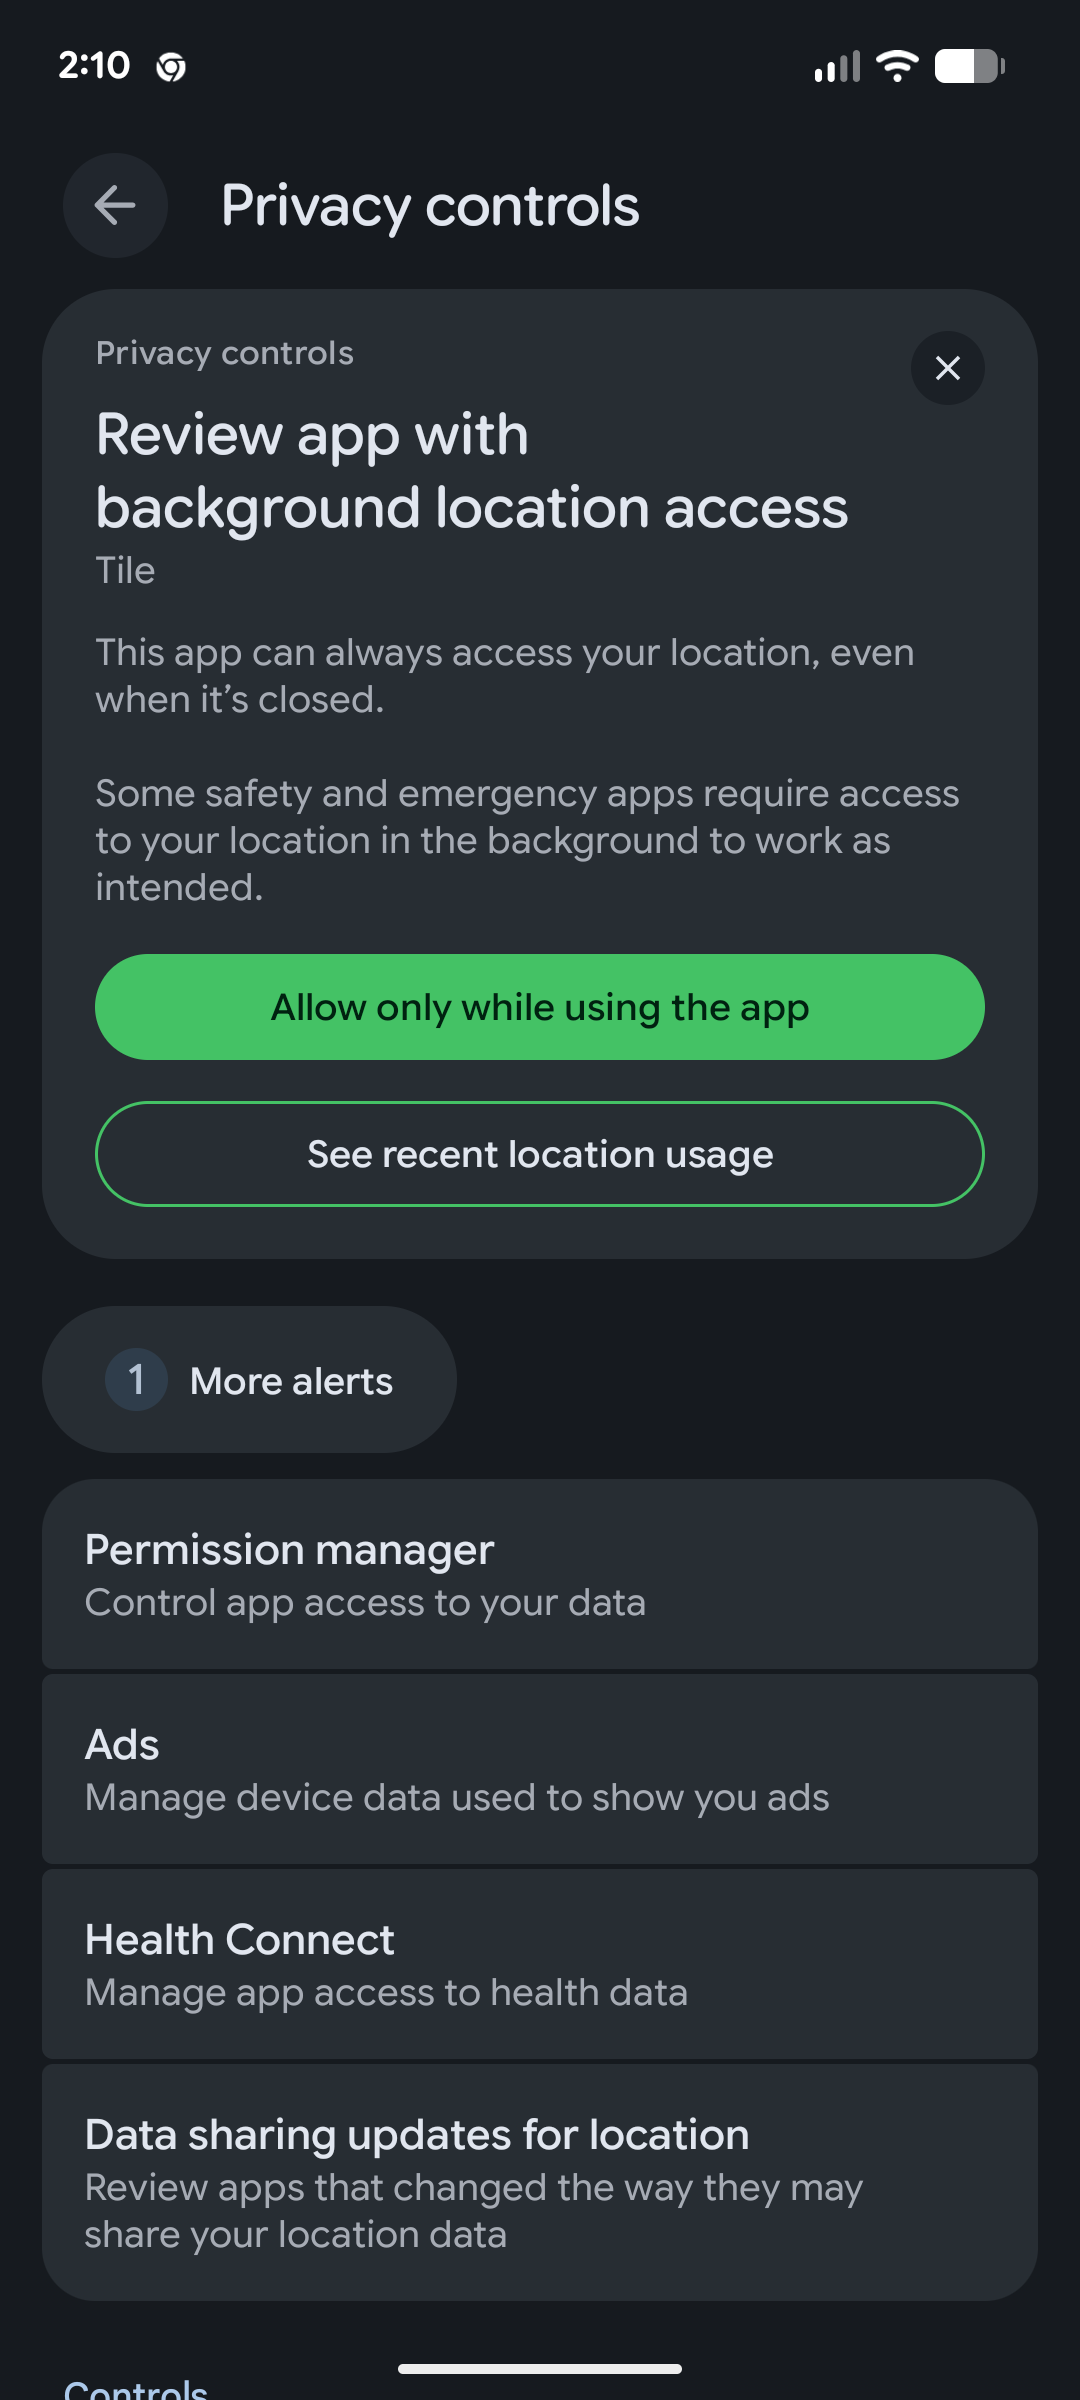
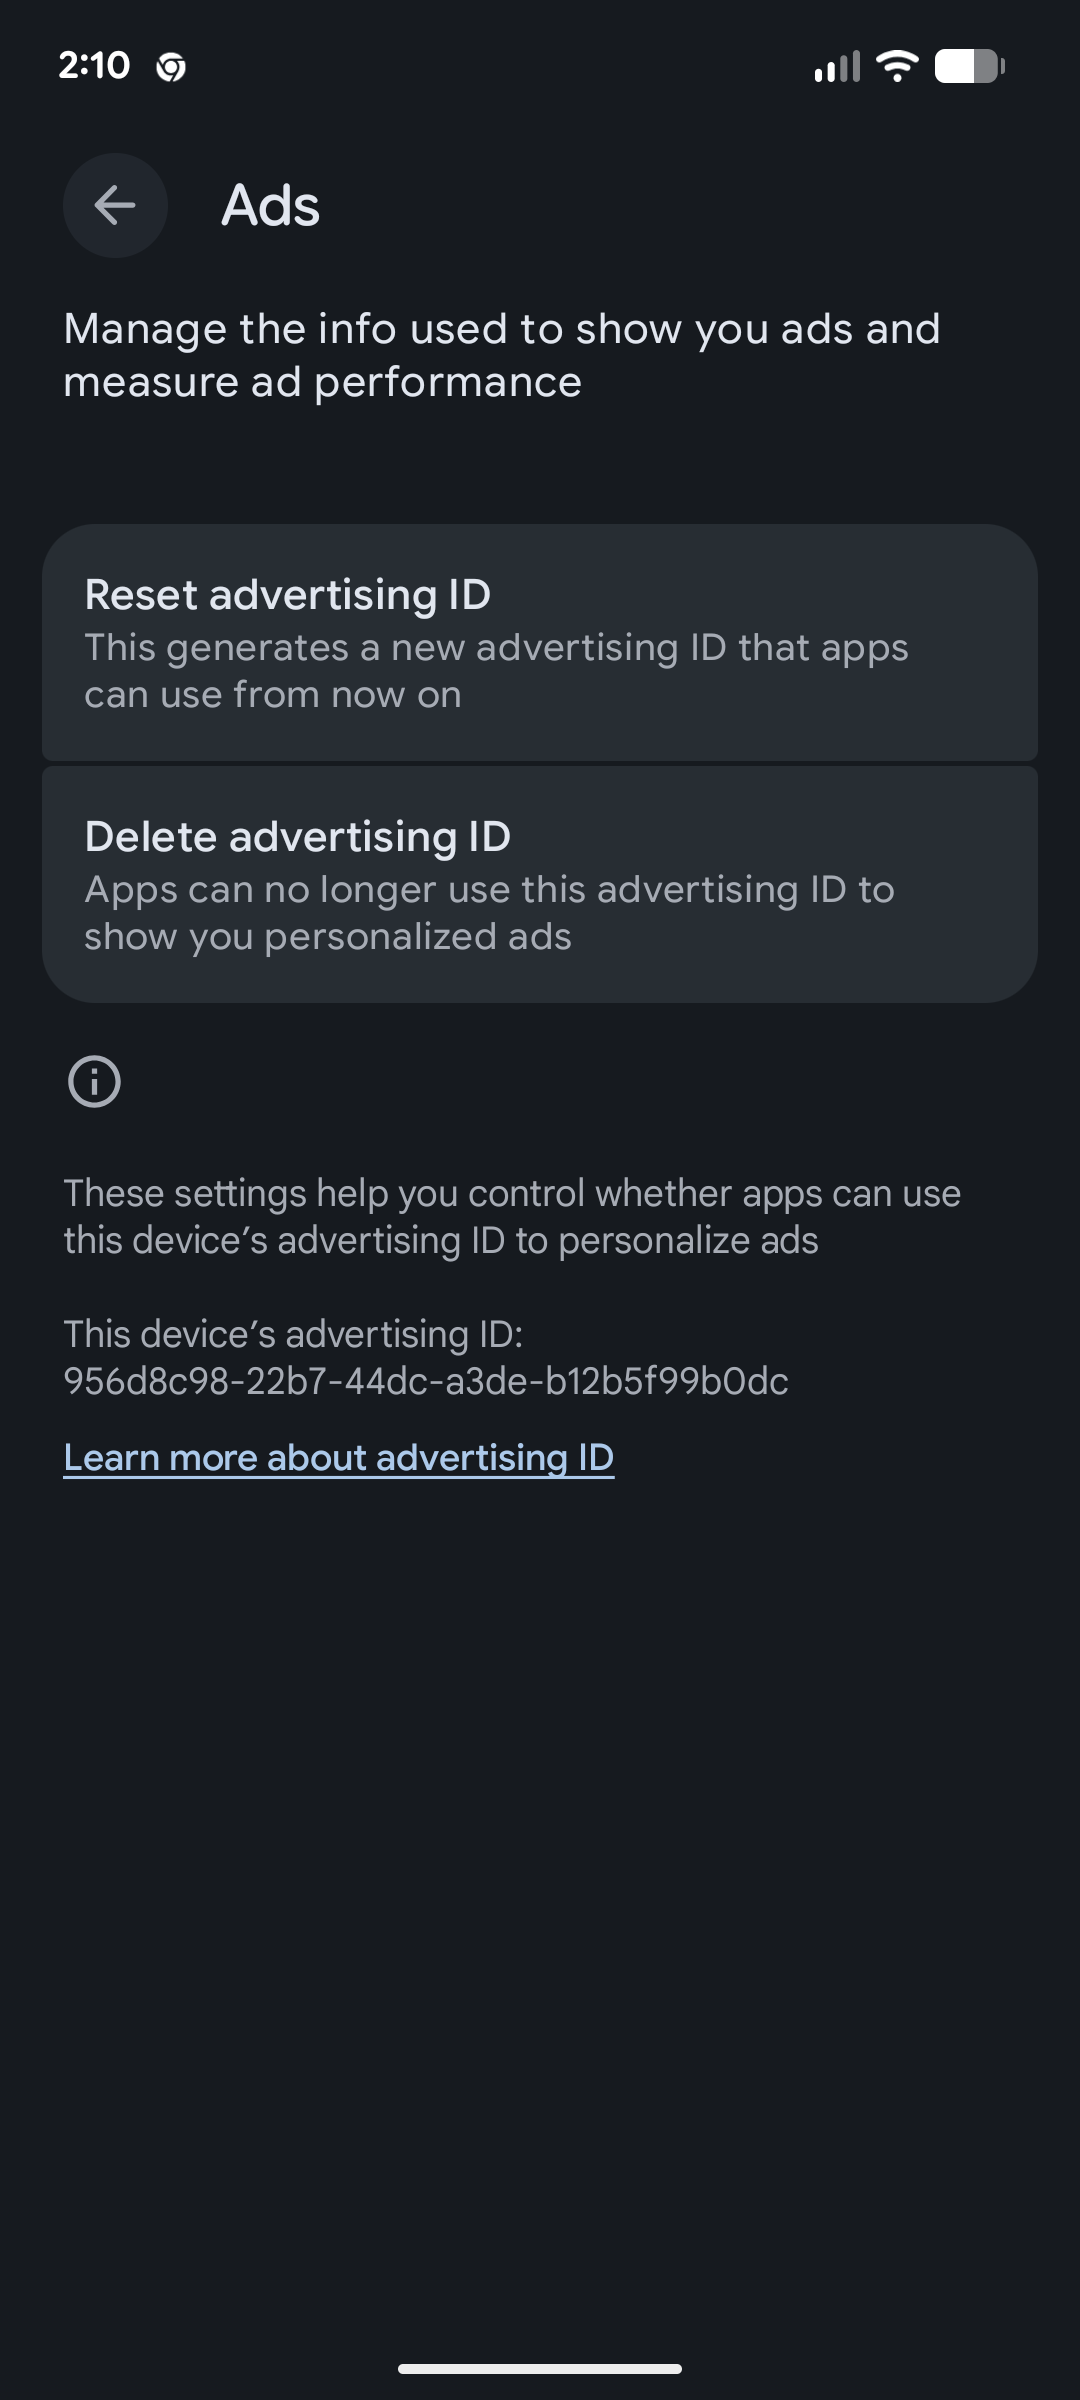
This article first appeared on KFF Health News and is republished here under a Creative Commons Attribution-NonCommercial-NoDerivatives 4.0 International License.
October 30, 2026RoseHealth News, KFF Health NewsNo commentsWhen Ashley Porter began slurring her speech one October day four years ago, doctors suspected a stroke. A spinal tap, an MRI, dozens of blood draws, another MRI, and a night spent at the hospital were followed, finally, by an answer: Porter had multiple sclerosis.
Her shock turned to outrage, she said, when she received the roughly $180,000 hospital bill, even though insurance covered most of it.
Porter and her husband have insurance through two separate employer plans yet have spent at least $75,000 a year — roughly a quarter of their gross income — on medical expenses since her diagnosis.
“It is terrifying,” said Porter, who works in transportation sales in the San Francisco Bay Area. “I can’t imagine having this disease and not making the kind of income that we make.”
With health insurance premiums and hospital prices rising faster than inflation, more than 40% of adults nationally struggle to afford their care and, like most, want the government to address it.
The average premium for a California family with employer-sponsored coverage has hit nearly $28,400 a year, up 24% since 2022, much more than workers’ wages. Amid skyrocketing healthcare costs, the gubernatorial candidates’ proposals remain short on specifics about funding or implementation to address this top priority for voters in the nation’s largest healthcare market.
“People are hungry for pretty aggressive action on healthcare spending,” said Kristof Stremikis, director of market analysis and insight at the California Health Care Foundation, a nonprofit philanthropic organization specializing in healthcare research and education.
“Regardless of who our new governor is and who our new state policymakers are in the next year, they have a mandate,” he said.
Nearly two-thirds of Californians worry about receiving an unexpected medical bill, surpassing financial concerns such as the cost of rent or food, according to a 2025 CHCF-NORC survey. Six in 10 said they or a family member had skipped care because of cost.
Democrat Xavier Becerra, the former U.S. health secretary who has a commanding polling lead in the race for governor, has vowed to negotiate lower drug prices and go after anticompetitive practices as he did as attorney general in a landmark antitrust settlement with hospital giant Sutter Health.
He has also said that Congress should restore an estimated $900 billion in federal Medicaid cuts and reinstate enhanced Affordable Care Act tax credits that President Donald Trump and the Republican-controlled Congress allowed to expire, causing insurance premium payments to increase for millions of Americans. Both are national Democratic priorities outside a governor’s purview.
Former Fox News host Steve Hilton, Becerra’s Republican opponent, has said he’d build on existing state laws governing price transparency and prescription drug middlemen known as pharmacy benefit managers to lower costs. And he wants to partially replace Medi-Cal, the state Medicaid program, with personal healthcare accounts of up to $10,000 a year — a concept unlikely to gain traction in a statehouse controlled by Democrats.
Both candidates declined multiple interview requests to discuss their health policies.


Healthcare Costs and Consolidation
From 1970 to 2025, U.S. health expenditures ballooned from $75 billion to a projected $5.7 trillion, rising nearly 40% from 2020. By 2032, the Centers for Medicare & Medicaid Services predicts, health spending will account for more than a fifth of the U.S. economy.
Payments to hospitals, doctors, and clinics account for much of the inflation, along with rising prescription drug prices. Research shows that escalating mergers among physician practices, hospital groups, and insurers further stifled competition and raised prices.
In the 2018 lawsuit Becerra filed against Sutter Health, he accused the health system of using its market dominance to drive up hospital prices in Northern California, where procedures cost as much as 30% more than in other parts of the state.
The Sacramento-based not-for-profit system, which admitted no wrongdoing, paid an unprecedented $575 million fine and agreed to stop certain business practices, including imposing “all-or-nothing” terms on insurers that forced them to contract with the system’s entire network of clinics and hospitals.
“It was the biggest victory in antitrust and hospitals ever,” said Richard Scheffler, director of the Nicholas C. Petris Center on Health Care Markets and Consumer Welfare at the University of California-Berkeley. A report by the center, which conducts economic research on health policy topics, formed the basis of Becerra’s suit.
“But things change,” Scheffler said.
While the settlement likely discouraged similar practices by other hospital chains, he said, any relief has since been eclipsed by rapid consolidation in the healthcare industry.
At a press event in October, Becerra said he would work with the next state attorney general to “continue to look at the types of practices in healthcare that drive up costs.”
Hilton has said that he wants to increase competition by producing more generic drugs through California’s CalRx initiative, which aims to cut drug prices. He has said he wants to allow consumers to pick cheaper, pared-down insurance plans and force healthcare providers to make their prices more transparent.
Hospitals Under the Scope
Health economists say rising healthcare costs eat up money that employers might otherwise use for raises or new hires, depressing wages. That can be a double whammy for workers already struggling to meet basic needs and, consumer advocates warn, could increase medical debt, which 40% of California adults already report carrying.
Kia Frazier-Hill and her husband didn’t expect to be among them. She knew it would be expensive when he landed in the emergency room and was hospitalized at an out-of-network facility.
The astronomical prices gave her sticker shock: $17,507 for a night in the intensive care unit; $427.89 for a test for flu, covid, and RSV, or respiratory syncytial virus; $2.60 for a single tablet of generic, regular-strength Tylenol. Their bronze-tier plan from Covered California, the state’s ACA insurance marketplace, paid the vast majority, nearly $60,000, but the $7,500 balance has been in collections for months.
“We’re drowning,” Frazier-Hill said. “It just doesn’t make any sense what they’re charging.”
Researchers have found that hospital prices are even higher in uncompetitive markets.
California is trying to corral such runaway health costs through its Office of Health Care Affordability, which has directed most health systems, hospitals, insurers, and large healthcare provider groups to hold their spending growth to 3.5% this year.
Hospital and doctor groups, which have donated to Becerra’s campaign, say the cap is too low and will limit patient care, not improve efficiency.
“Hospitals have a mission to take care of people, save lives, and that costs money,” said Amber Ott, senior vice president of financial policy for the California Hospital Association, which is challenging the affordability board’s caps in court. “It’s hard to look at just one piece of the ecosystem and say that’s where the problem is.”
While hospitals are not the only drivers of high costs, they are the largest. According to the state, at least 40% of total health spending by commercial insurance plans went to hospitals in 2024, the latest data available.

Low-Hanging Fruit
As rising healthcare costs have driven up spending by public insurance programs and put pressure on state budgets, states have taken more of a lead in tackling affordability. But they are limited in what they can do. While California has led on prescription drug price transparency and negotiating more competitive marketplace plan rates, it lags other states in some respects, said Sabrina Corlette, a co-director of the Center on Health Insurance Reforms at Georgetown University.
“There’s a lot more they could do to rein in underlying drivers of healthcare costs,” she said of state policymakers.
Some states, for instance, have banned certain facility fees, which allow hospitals to charge higher prices than unaffiliated doctors’ offices even when services are rendered at outpatient clinics that they own. Corlette said such fees increase patient costs while incentivizing hospitals to gobble up more clinics and physician practices.
Oregon capped the payments its public employee health plans make to hospitals, reducing patients’ out-of-pocket spending on outpatient procedures by nearly 10%. Rhode Island limits hospital cost growth through an annual rate review of state-regulated health plans. California has done neither.
California healthcare advocates and researchers say there’s plenty of low-hanging policy fruit that could bring consumers more immediate relief. Insurers and providers could work to automate notoriously inefficient prior authorization procedures, while lawmakers could mandate shorter insurer response times to prior authorization requests, as New Jersey and Vermont have done.
The legislature could also broaden bans on anticompetitive contracting, much like Connecticut and Texas, or expand on Los Angeles County’s program to purchase and forgive residents’ medical debt.
Heath policy experts say even those relatively modest ideas would be a heavy lift in Sacramento, where the industry spends tens of millions of dollars annually to influence lawmakers and state agencies.
“It’s a big, complicated system, and the money is so gigantic,” said Glenn Melnick, a healthcare economist at the University of Southern California. “At some point, the legislature has to hold the line and say, ‘Look, it is the golden goose, but we’re going to have to feed it a little bit less.’”
This article first appeared on KFF Health News and is republished here under a Creative Commons Attribution-NonCommercial-NoDerivatives 4.0 International License.
October 29, 2026RoseHealth - The New York Times, NYT > HealthNo commentsOctober 29, 2026RoseHealth News, KFF Health NewsNo commentsPAGE, Ariz. — Doug Herrera still lives in the house his father built, though his dad died some time ago from cancer. Herrera wonders if that illness could have been linked to pollutants from nearby uranium mining. Now, he worries that a possible new neighbor — a proposed $10 billion mega data center — could imperil his health.
“I’m a patriot, but I’m highly against the data center,” Herrera, 64, said from his front porch near a yard sign that reads “No Data Centers.”
“There is light pollution, sound pollution. The temperature is going to rise,” he said.
Page is a gateway to iconic Southwestern landscapes of arid desert studded with Joshua trees and towering red-rock formations. While the City Council approved the sale of land for a data center, the developer needs zoning and other approvals. Residents concerned about possible health effects have signed petitions and mobilized to oppose construction.
The boom in data centers is dividing communities such as Page and turning future construction into a flash point in the midterm elections. The leading candidates in the close race for Arizona’s 1st Congressional District are at odds over any new centers there, and the state’s attorney general has called for a pause on new approvals and building.
Emerging research into data centers’ possible health effects is adding grist to the various state fights, giving ammunition to Democrats and some Republicans who’ve broken party ranks to oppose the sprawling complexes.
It has also put some incumbent politicians who have supported data center expansion in unexpectedly vulnerable positions in reliably red states like Ohio and Texas, where the megabuildings now operate by the hundreds.
“Two years ago, a lot of these data centers went up and there was not an organized, watchful opposition,” said Lee Hannah, a political science professor at Wright State University in Dayton, Ohio.
“That opposition has come up in a grassroots way so quickly that decisions made a year ago by local officials or state governments to get behind a data center are suddenly career-ending.”
The hyperscale centers house infrastructure to power AI, with servers that sprawl over tens of thousands of square feet or more. The city of Page approved the sale of 500 acres for the proposed data center, though the location within that acreage hasn’t been decided. The area sits on open land studded with blackbrush and native grasses near Horseshoe Bend, an iconic curve of the Colorado River that has long been popular with tourists.
Data centers gobble up electricity and rely on backup gas generators during times of peak energy demand. The resulting air pollution has been linked to heart conditions, respiratory issues, and elevated cancer risks, according to a number of environmental studies.
Emissions from the centers could cause nearly 1,300 deaths annually by 2030 and an annual public health burden of more than $20 billion in 2028, based on modeling led by researchers at the University of California-Riverside.
Cooling components can contain what are called forever chemicals, synthetic substances that accumulate in human tissue, according to advocacy and environmental groups. And the hum and whir of generators and heating and air conditioning systems can exceed 90 decibels, which can harm hearing.
Data centers are lit up for operations and security, creating light pollution that can increase the risk of chronic disease, the groups say. The megafacilities also create what are known as data heat islands, which are higher-temperature zones caused by intense energy demands.
“We’re just starting to see the very early edge of the wave of the research into health impacts of data centers,” said Alison Steele, executive director of the Environmental Health Project, a nonprofit public health organization. “By the time we have a substantial volume of research it’s going to be too late, because the decisions are being made now.”
A trade group for the data center industry said a review of the largest data center market — Virginia — found that use of backup power sources, including diesel generators, is minimal, and that existing state and federal regulations limit potential emissions or impacts.
“Data centers are committed to being responsible partners where they operate,” said Dan Diorio, executive vice president of state policy and government affairs at the Data Center Coalition.
It Cuts Across Politics
Mounting concerns about data centers are dividing candidates and pitting some GOP contenders against President Donald Trump, who supports the facilities’ construction as vital for economic growth.
Two in 3 Americans oppose the construction of new data centers in the U.S., according to an October Washington Post-ABC News-Ipsos poll.
Such political standoffs are happening largely in states that Trump won in 2024, where most new data center capacity has been proposed. About 1,400 data centers operate in the U.S., and an additional 2,000-plus are planned.
Sixty percent of data center capacity under construction is in states Trump won by five percentage points or more, according to Cleanview, a market intelligence company. Excluding Virginia, 92% is in states the president won.
Hannah said the uptick in construction has put Trump’s coalition at particular risk because data centers are often built in rural areas, where the president has often enjoyed insurmountable margins of support.
“This is where most of the data centers go,” Hannah said. “They go into red states, because Republicans are less critical of economic opportunity. If it promises jobs and money, they’re all in.”
In Page, signs opposing construction pepper front yards.
The opposition to more data centers in the state could pose political risks for GOP House candidate Jay Feely, who won his primary with an endorsement from Trump. He says they are key to keeping up with China. Democratic opponent Amish Shah wants a pause on new construction in their district.
The House seat they’re vying for is considered competitive, and the contest could be pivotal in determining which party gains House control after the Nov. 3 midterms.
In Arizona, 57% of registered voters oppose construction of more large data centers, according to an August opt-in online poll of 1,040 registered voters by Noble Predictive Insights.
More Than Costs
Photos from across the nation featuring politicians at groundbreaking ceremonies for data centers held only a year or two ago are now campaign fodder.
That has become a big problem for some elected leaders in Ohio, where more than a dozen local referendums or initiatives related to construction of the facilities will appear on ballots — the most of any state.
The issue has forced its way to the forefront of the state’s marquee U.S. Senate race. Former Sen. Sherrod Brown, a Democrat, is hoping to return to Congress with pointed attacks against Republican Sen. Jon Husted over the matter.
Roughly $2.5 billion in state and local tax breaks over the last decade have prompted Meta, Amazon, Google, and other tech companies to erect dozens of data centers across Ohio. That boom has spurred protests across the state, organized by local residents who are worried about the health, environmental, and financial impact of the structures.
Brown has pinned the blame on Husted directly with ads airing widely across Ohio that call him “the face of data centers.”
“They’re devouring our farmland, sucking up our water, and using our energy,” Brown says in one recent video.
A memo circulated by the National Republican Senatorial Committee in August and obtained by Politico described Brown’s critiques as a big problem for Husted.
“More than any other thing in this race, data centers are the anchor hanging around Husted’s neck,” warns the Aug. 18 memo, which was shared with artificial intelligence companies.
Husted has rebuffed these critiques by framing the construction of data centers as a local issue. More recently, he has said he wants to make sure that the companies building data centers pay for infrastructure costs, including energy.
In a statement, Husted spokesperson Tom Evans reiterated that point, saying the senator believes “data centers should remain a local decision.”
It’s not just costs that voters care about. An early-October opt-in survey of 1,650 Ohio adults by Ohio Northern University and SurveyUSA found that 55% were opposed to data center construction. About two-thirds had a negative opinion of data centers’ impact on their community’s environment, and about half said the same about their impact on quality of living.
Opponents of data centers cite noise, air, and water pollution as a concern, according to a Gallup poll. Americans are more opposed to data centers in their area than nuclear power plants.
The air pollution comes from gas turbines and diesel generators that have been linked to cardiovascular problems, asthma, and other health risks. Cooling system chemicals, heavy metals, and construction runoff can enter the water supply or rivers.
“When they are fired up and powered by diesel, they emit a lot of air pollution like nitrogen oxide, and this pollutant can travel around the community and to those downwind,” said Shaolei Ren, an electrical and computer engineering professor at the University of California-Riverside.

In Page, residents in July voted out the mayor amid backlash over the Council’s approval of the land sale for the data center. Opponents of data centers say it’s a warning to candidates in the midterm elections who back new construction.
Some residents in this picturesque town of about 7,000 people remain worried that the health effects could plague them if the project goes forward. Jan Boehme lives in a neighborhood close to the proposed site. From her front lawn with its “No Data Center” sign, she said she is concerned that a data center could become her new neighbor — and cause harms such as hearing loss.
“We’re against it,” she said. “In this area, there are a lot of houses, and I’m concerned about all the noise.”
KFF Health News is a national newsroom that produces in-depth journalism about health issues and is one of the core operating programs at KFF—an independent source of health policy research, polling, and journalism. Learn more about KFF.This article first appeared on KFF Health News and is republished here under a Creative Commons Attribution-NonCommercial-NoDerivatives 4.0 International License.
October 29, 2026RoseHealth News, KFF Health NewsNo commentsStephanie Rowell was standing on her parents’ front porch in July when a wasp stung her left arm.
She said that almost immediately her arm felt like it was “on fire,” her body started itching all over, and her face became swollen and red.
Rowell, 53, took Benadryl, and her father started driving her to the nearest emergency room, about 25 minutes away. But after driving for 10 minutes they spotted a TruHealthNow urgent care facility in Purcellville, Virginia, and decided to stop, hoping she would get help faster.
“I thought I was going to die,” she said, recalling that she felt her throat tighten and found it harder to breathe.
Rowell, a manager at an agritourism business who lives in Round Hill, Virginia, has been uninsured since 2025, when she said she could no longer afford to buy coverage on her own.
After she checked in and disclosed that she did not have health insurance, Rowell said, a nurse practitioner saw her in an exam room and quickly diagnosed anaphylaxis, a severe and potentially life-threatening allergic reaction.
She said the nurse practitioner advised her that she needed a shot of epinephrine to reverse her symptoms.
Then the bill came, via a medical assistant.
“The medical assistant apologized and said I had to pay $400 for the shot up front,” Rowell said.
The Medical Service
Epinephrine is a naturally produced hormone, and a synthetic version is used as an injectable medication to treat severe allergic reactions, typically delivered via a single-dose prescription device called an EpiPen. It can prevent anaphylaxis from developing into anaphylactic shock, a life-threatening condition that occurs when the reaction causes a dramatic drop in blood pressure.
Because patients sometimes experience a recurrence of anaphylaxis after the initial reaction, it is recommended that patients be monitored in the hours after receiving epinephrine.
In addition to the injection, the urgent care’s staff checked Rowell’s vital signs, including her blood pressure, and a medical assistant monitored her for 30 minutes after she received the shot, according to Manbir Takhar, TruHealthNow’s medical director.
The Bill
$605: $400 for the medication, a $40 fee to administer it, and $165 for the visit to the urgent care center.
The Billing Problem: Emergency Care or Urgent Care?
Rowell said she was stunned that she was expected to pay before she received the shot of epinephrine. She returned to the waiting area to retrieve her wallet from her dad.
After she handed over her debit card, she said, the medical assistant gave her the shot. Within a few minutes, she could feel her throat loosening and her symptoms eased.
“I asked, ‘If I didn’t have the money, would you have just let me die?’” Rowell said. “And they said, sorry, that is their policy.”

Officials at TruHealthNow, which privately owns and operates eight urgent care centers in Northern Virginia and Maryland, said Rowell was told its policy in emergencies is to first provide treatment before handling billing. “Our policy is we give the shot and worry about the money later,” Preet Takhar, TruHealthNow’s CEO, said in an interview with KFF Health News.
The company officials confirmed Rowell was asked to pay before she received the shot. They said the nurse practitioner first determined Rowell’s condition was stable and that she was asked for payment as the injection was being prepared.
The request for payment did not delay administering the shot, said Manbir Takhar, who is married to Preet Takhar.
“The patient was stable, and that is why we took the payment then,” she said.
Federal law requires hospital emergency departments to stabilize anyone who shows up, regardless of ability to pay. But urgent care centers generally don’t fall under that law unless they are owned by hospitals, said Barry Furrow, director of the health law program at Drexel University in Philadelphia.
Urgent care centers have proliferated across the country in recent years, offering quick access to care, especially for people who don’t have a regular physician or can’t immediately see one, and particularly after hours and on weekends. The clinics usually take insurance and charge patients who don’t have coverage.
More than 15,000 urgent care centers handled about 185 million patient visits in 2025, according to the Urgent Care Association, a national trade group.
Urgent care centers offer a wide range of primary care services, treating conditions such as sore throats, flu, sprained ankles, and minor cuts. While services vary, they are not intended to treat life-threatening emergencies such as heart attacks or traumatic injuries.

Yet people sometimes show up at urgent care centers when they need emergency care, usually because they do not realize the seriousness of their condition, said Alan Ayers, an urgent care industry consultant.
While urgent care centers, like most doctors’ offices, ask for an insurance card or payment up front, that should not happen for patients needing emergency help, he said.
“Collecting a copay at check-in is standard across outpatient medicine, and it’s a separate question,” Ayers said. “For a sore throat, it doesn’t matter much. For anaphylaxis, it should never come up.”
Doctors also face an ethical obligation to treat patients facing an emergency if they have the capability, without asking for up-front payment, said Arthur Caplan, professor emeritus and past head of the medical ethics division at the New York University Grossman School of Medicine.
In a lifesaving situation, “you don’t need to have a patient go fumbling around for a credit or insurance card,” he said. “If you have the skill to take care of someone, you should.”
Medical experts say patients should generally know when to seek care at a hospital instead of an urgent care facility. For example, if they have trouble breathing or are experiencing chest pain, they should head to the ER. But some cases are not as clear-cut.
“Patients do not always know the severity of their condition when they decide where to go for care, and a patient’s condition can change,” said Steven Sellars, CEO of the Urgent Care Association.
Sellars said urgent care operators establish their own policies for what to do when patients need emergency care, such as when to transfer patients to a hospital.
The Resolution
Rowell went home after leaving the urgent care center. Her brother stayed with her to watch her for complications. “I felt wiped out,” she said, noting it took several days until she felt completely better.
Her daughter posted a summary of her experience on a Facebook community group’s page, eliciting hundreds of comments.
Rowell said she wasn’t upset at the price but believed she shouldn’t have had to pay before receiving the epinephrine. The price for a generic EpiPen is about $175, according to GoodRx.
She said she now carries an EpiPen.

The Takeaway
When in doubt as to whether you are having a medical emergency, always err on side of caution and go to the nearest ER or call 911, said Ryan Stanton, president of the American College of Emergency Physicians.
People with life-threatening allergies should get a prescription for an EpiPen to keep at home or with them, said Stanton, who is an ER physician in Lexington, Kentucky.
Bill of the Month is a crowdsourced investigation by KFF Health News and The Washington Post’s Well+Being that dissects and explains medical bills. Since 2018, this series has helped many patients and readers get their medical bills reduced, and it has been cited in statehouses, at the U.S. Capitol, and at the White House. Do you have a confusing or outrageous medical bill you want to share? Tell us about it!
This article first appeared on KFF Health News and is republished here under a Creative Commons Attribution-NonCommercial-NoDerivatives 4.0 International License.
October 28, 2026RoseHealth - The New York Times, NYT > HealthNo commentsOctober 28, 2026RoseHealth News, KFF Health NewsNo commentsKarlo Campana is usually outnumbered these days. He has three young kids under age 4. On a recent Saturday, he played a mini game of basketball with his two older kids in their Southern California home, shooting a ball into a hoop on the door, while his baby boy watched from his bouncy chair.
Campana took paid time off in May after the birth of his son — just as he did for his daughters.
“You need that adjustment period,” he said. Campana, who works at an ad agency, said having the time off not to think about work — or worry about losing income during that time — was crucial for him and his family during a sleep-deprived period.
“My wife isn’t doing it on her own,” he said. “She doesn’t feel like she’s alone on this journey. She feels like she has support.” He jokes that by kid No. 3 he thought he had nailed diaper changes without getting peed on — but he was wrong.
“The benefits are I get to spend time with each of them when they were in the infant stage, the baby stage, and I get to hold them and, you know, change the poopy diapers,” he said. “ It’s like the funny moments of, like, being a parent, like, ‘This is it right here, you’re in the thick of it.’”
Campana is among a growing number of fathers who take leave to bond with a new child in states that offer paid family leave programs — and are part of a larger cultural shift that has seen dads handling more caregiving duties. In California — as in several other states — men make up about half of bonding claim applications. Last year, men even surpassed women — as in Colorado and Washington — for the first time in the state’s history. This trend comes at a time when the federal government has said it wants Americans to have more babies, and families report affordability is an obstacle to raising them.
No federal law guarantees paid parental leave, but California is one of 14 states, plus Washington, D.C., that have passed legislation to enact paid family leave programs — and in many of those places, more dads are opting in.
“We’re in a very different place in terms of our understanding of gender roles, of paternity leave, of dads’ roles than we were 20-plus years ago,” said Molly Weston Williamson, policy director at Paid Leave for All, an organization that advocates for paid family leave policies.
California’s program offers, within a year, up to eight weeks of paid bonding leave for parents after a birth or adoption. That’s on top of six to eight weeks of paid disability leave that moms get to recover after birth.
Research has shown that paternity leave confers benefits beyond allowing a father extra time to bond with a new child: It has positive effects on the whole family, including better health outcomes for both parents. Paid parental leave has also been linked to lower odds of postpartum depression and a decrease in infant mortality rates.
In California, men accounted for 51% of bonding claims filed in 2025. It’s a massive shift from when the state program started in 2004, and men made up about 18% of claim applications.
States fund paid family and medical leave with different combinations of employer and employee contributions; California is among six states where family leave is entirely funded by employee payroll deductions.
In addition to changing gender norms, Weston Williamson said, other factors likely contribute to the increase in claims by men in the state: greater awareness about the program and recent changes to the benefit.
In 2025, the state boosted the amount of income a worker can recoup while on family leave. Now, in California and other states, the leave benefit can be as high as 90% of their regular salary.
“That makes it a realistic option for a lot more families, and I think we’re seeing dads and moms responding to that change,” Weston Williamson said. Still, she said, there’s a lot the new data about dads isn’t telling us.
“We’re getting one particular vantage point into this data, which is useful and valuable, but it’s only telling us sort of part of the story, and we’d need other kinds of information to better understand the full picture,” Weston Williamson said. “Is it that more dads are working and therefore are potentially eligible for these benefits? Is it that women are deciding not to take leave?”
While private employers can offer their own paid leave as a benefit, this data reflects only people who took leave through the state.
A spokesperson for the California Employment Development Department, which administers the state family leave program, said the department couldn’t provide definitive reasons for the increase in bonding claims by men.
One thing is clear: The growth in these states comes as more parents are feeling strained economically. President Donald Trump has said, “We want more babies,” and has promoted policy initiatives like expanding access to in vitro fertilization and offering investment accounts for newborns.
“People really are very worried about the affordability of kids,” said Jeremy Pope, a professor of political science at Brigham Young University.
In 2025, 7 in 10 Americans said raising children had become unaffordable, according to the American Family Survey out of Brigham Young University. It was the biggest single-year jump since the survey started more than a decade ago.
“I don’t think they want government involved in the decision to have kids,” Pope said. “But they worry a lot about how much it costs and they would like to see ways of making those costs smaller or getting help with those costs.”
The Pew Research Center found in a recent survey that among full-time working parents who are not self-employed, 84% said paid parental, family, or medical leave would be “extremely or very helpful” to them, but only half said it was available to them.
Dad-of-three Campana said he initially wasn’t sure if he should take paternity leave because of lingering gender stereotypes.
“ I felt guilty, for sure,” Campana said. “ I think dads maybe feel they need to be the provider. They need to be the ones that are only helping their family by bringing money or working.”
Campana said that when he was growing up, his father worked three jobs. “It was hard for him to be present, and I think that’s the one thing now — it’s like, ‘No, be present. Be there for your kids.’”
This article is from a partnership that includes LAist, NPR, and KFF Health News.
KFF Health News is a national newsroom that produces in-depth journalism about health issues and is one of the core operating programs at KFF—an independent source of health policy research, polling, and journalism. Learn more about KFF.This article first appeared on KFF Health News and is republished here under a Creative Commons Attribution-NonCommercial-NoDerivatives 4.0 International License.